
Submucosal Lesion? Everything You Need to Know in 2026
Most are benign, can be safely monitored, and when needed, resected via endoscopy.

Submucosal lesions appear as "bumps" beneath the surface of the digestive tract.
TL;DR (Quick Summary)
Most important:
- • The majority of submucosal lesions are benign: lipomas, leiomyomas, cysts…
- • Many don't grow or cause symptoms and are simply monitored without intervention.
When to act?
- • If they measure >2 cm, grow, cause discomfort, or endoscopic ultrasound suggests risk (GIST, NET).
- • Resection is often performed via advanced endoscopy, without open surgery.
Submucosal lesion? If you've just read this term in your colonoscopy or gastroscopy report, take a deep breath: the vast majority are benign and don't require immediate treatment. They're also called subepithelial lesions (SEL), and in this article I'll explain what they are, when it's appropriate to study them thoroughly, and how they're managed in 2026 with advanced endoscopy.
Quick Index
- • What are submucosal or subepithelial lesions?
- • Most common types (mostly benign)
- • Lesions in esophagus and stomach
- • Lesions in colon and rectum
- • When to study thoroughly (and when to monitor)
- • The key role of endoscopic ultrasound (EUS)
- • Treatment options: endoscopy vs surgery
- • What you can do starting today
- • Quick FAQ
What are submucosal or subepithelial lesions?
Imagine the digestive tract (esophagus, stomach, intestine) as a multi-layered tube. The innermost layer is called the mucosa and is what we see directly with the endoscope. Beneath it are the submucosa and muscle layer.
A submucosal or subepithelial lesion is a "bump" that originates beneath the mucosa. From the outside, it looks like an elevation covered by normal mucosa (without ulceration, without striking color change), but the endoscopist notices it's "not a classic polyp": it's firmer, deeper, as if something underneath is pushing toward the lumen. 1
Most common types (mostly benign)
Reassuring message
In large series of subepithelial lesions, only 3–10% had malignant potential. The vast majority are lipomas, leiomyomas, cysts, small stable neuroendocrine tumors, ectopic pancreas, or even inflammatory remnants. 2 3
The "classic benign ones"
Lipomas: fat accumulations beneath the mucosa, very common in the right colon. They're soft, hyperechoic on endoscopic ultrasound, and require no treatment unless they cause symptoms (extremely rare). 4
Leiomyomas: smooth muscle tumors, typical in the esophagus. They appear as firm, well-defined lesions, and in the esophagus are almost always benign (esophageal GISTs are exceptional, <1%). 5 6
Cysts, ectopic pancreas, granular cell tumors, schwannomas: rare lesions but usually benign, identified with endoscopic ultrasound and, if necessary, biopsy. 7
Those that need monitoring or resection
GIST (gastrointestinal stromal tumor): the best-known one with malignant potential. Typical of the stomach, though it can appear anywhere. Small GISTs (<2 cm) without aggressive features can be monitored; large ones or those with risk characteristics are resected. 8 9
Neuroendocrine tumors (NET): common in rectum and stomach. Small ones (<10 mm, well-differentiated) in the rectum can be resected via mucosal resection (EMR) with excellent results. Larger ones or those with aggressive criteria require more complete study. 10 11
Lesions in esophagus and stomach: what to expect?
Esophagus
The vast majority of esophageal subepithelial lesions are benign leiomyomas. They're hard, well-defined, and grow from the muscle layer. Esophageal GIST is extremely rare (<1% of all GISTs). 5 12
If a leiomyoma is large (>3–5 cm) or causes symptoms (dysphagia, pain), it can be resected using advanced endoscopy techniques like STER (submucosal tunneling endoscopic resection) or EFTR (endoscopic full-thickness resection), with very high success rates and few complications. 13 14
Stomach
Here things are more varied: lipomas, ectopic pancreas, neuroendocrine tumors, leiomyomas… and GIST. Endoscopic ultrasound (EUS) is key to distinguishing them: it measures size, sees the layer of origin, detects echogenicity (lipomas are very bright, GISTs are usually hypoechoic). 8 15
Guidelines from the European Society of Gastrointestinal Endoscopy (ESGE) and the American College of Gastroenterology (ACG) agree: small gastric lesions (<1–2 cm), without alarm signs, can be monitored with follow-up endoscopies. If they grow, they're resected. 16 17
Lesions in colon and rectum: increasingly common findings
With increased screening colonoscopies, more colonic subepithelial lesions are being detected. The good news: most are lipomas, lymphangiomas, inflammatory polyps, or even retained fecaliths (which can be mistaken for tumors). 4 18
In a series of 105 colorectal subepithelial lesions, only 2.9% were malignant, and all "soft" lesions on endoscopic palpation were benign. 2
Lesions requiring monitoring are: rectal neuroendocrine tumors (common, but most small and low-grade), colorectal GISTs (rare), and occasionally lymphomas or metastases. 10 19
When to study thoroughly (and when monitoring is sufficient)?
Criteria for complete study
- • Size ≥2 cm.
- • Growth during follow-up.
- • Surface changes: ulceration, erythema, depression.
- • Symptoms: pain, bleeding, obstruction.
- • Endoscopic ultrasound suspicion of GIST or high-grade NET.
If your lesion is small (<1 cm), soft, without mucosal changes, and endoscopic ultrasound shows a well-defined lipoma or leiomyoma… you can rest easy. In long-term follow-up studies, these lesions almost never grow or cause problems. 3 20
The key role of endoscopic ultrasound (EUS)
Endoscopic ultrasound is like doing an "ultrasound from inside" the digestive tract. It tells us:
- Which layer the lesion originates from (mucosa, submucosa, muscle…).
- Whether it's solid, cystic, or fatty (hyperechoic → lipoma; hypoechoic → GIST, NET, leiomyoma).
- Exact size (often more precise than endoscopy).
- If needed, guides fine-needle aspiration/biopsy (FNA/FNB) to obtain tissue for histological diagnosis. 8 21
In my daily practice, EUS is the test that "puts a name" to the lesion and decides whether we monitor, resect, or request further studies.
Treatment options: advanced endoscopy vs surgery
Years ago, many submucosal lesions were operated on with open or laparoscopic surgery. Today, most can be resected endoscopically, thanks to techniques like:
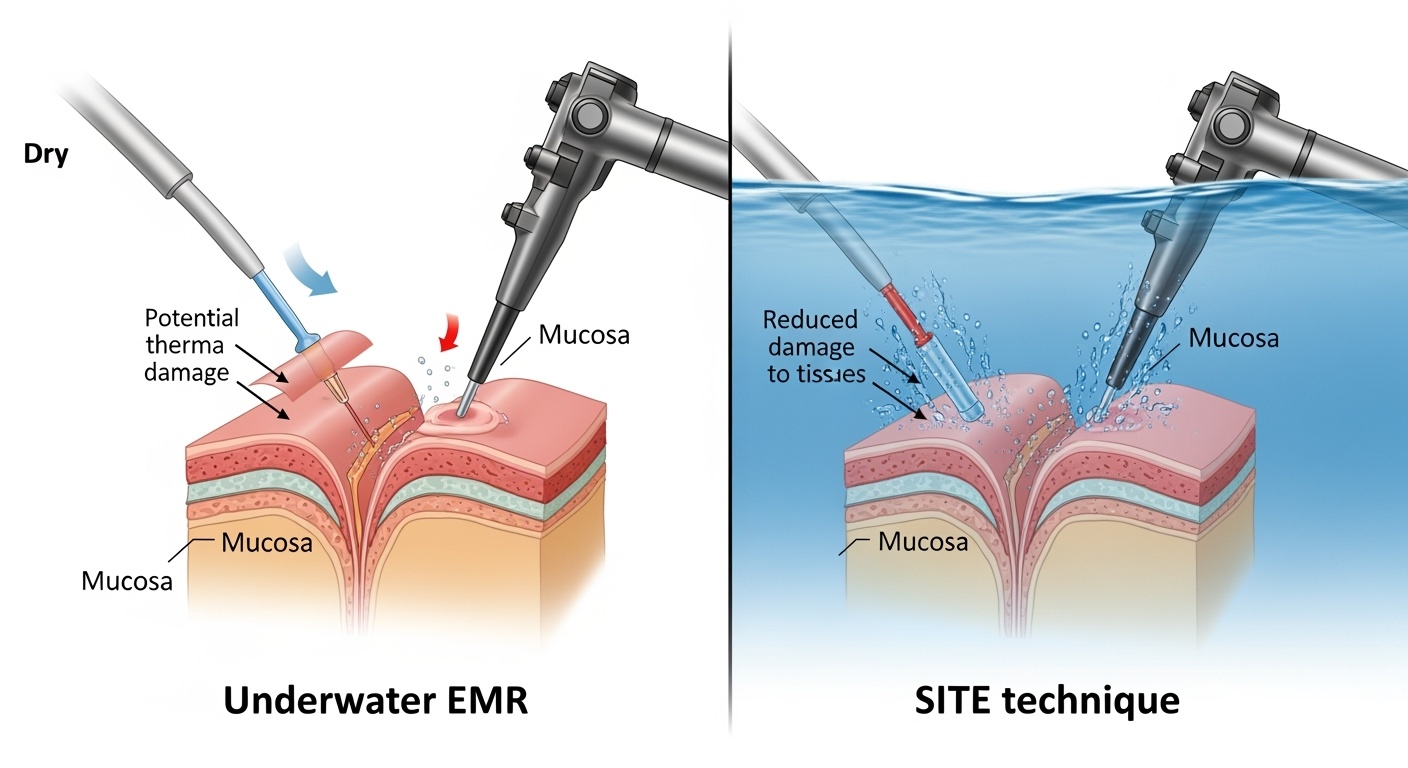
Mucosal resection (EMR)
For small, superficial lesions (mucosa + superficial submucosa). Very useful in rectal neuroendocrine tumors <10 mm or polyps with submucosal component. 22 More info: Endoscopic Mucosal Resection (EMR).
Endoscopic submucosal dissection (ESD)
The gold standard technique for large mucosal/submucosal lesions. Allows en bloc resection, clear margins, and complete analysis. In my experience, it's the technique of choice for large colorectal polyps with suspected submucosal invasion. 23 More info: Endoscopic Submucosal Dissection (ESD).
STER, EFTR, tunneling resection
For lesions originating in the muscle layer (esophageal leiomyomas, some small GISTs): a submucosal "tunnel" is created, the tumor is reached, resected, and closed. Excellent results in referral centers. 13 14
In a recent review of endoscopic resections of colorectal subepithelial lesions, en bloc resection was achieved in ~97% and complete resection in ~89%, with low complication rates (perforation <5%, controllable bleeding). 3
Have a subepithelial lesion? We'll evaluate your case and decide the best plan: monitoring, endoscopic ultrasound, or endoscopic resection.
What you can do starting today?
4-step plan
- 1) Don't panic: most are benign.
- 2) Request a copy of the endoscopic report (with photos if possible).
- 3) If the lesion is ≥1 cm or there are doubts, consult to consider endoscopic ultrasound.
- 4) If it's small and without risk criteria, plan follow-up and breathe easy.
Related readings that may interest you


A personal touch
I've seen hundreds of subepithelial lesions in my daily practice. The vast majority end up being benign, but I understand the report can generate uncertainty. My job is to clearly explain what you have, what risk it carries, and what options you have. And if resection is needed, we do it with the most minimally invasive technique possible.

FAQ: quick questions about submucosal lesions
What is a submucosal or subepithelial lesion?
It's a bump that appears beneath the superficial layer of the digestive tract. Most are benign: lipomas, leiomyomas, small neuroendocrine tumors, or cysts.
Are all submucosal lesions dangerous?
No. The vast majority are benign, and many don't grow or cause symptoms. Only a small percentage (large GISTs or neuroendocrine tumors) have malignant potential.
When should a subepithelial lesion be resected?
When it measures more than 2 cm, grows during follow-up, causes symptoms, or endoscopic ultrasound suggests risk (GIST, NET). Small lesions without alarm signs are monitored.
How are these lesions removed?
Many can be resected via advanced endoscopy (mucosal resection, ESD, or techniques like STER/EFTR). Surgery is reserved only for very specific cases.
Scientific references (clickable)
- Jacobson BC, et al. ACG Clinical Guideline: Diagnosis and Management of Gastrointestinal Subepithelial Lesions. Am J Gastroenterol 2023;118(1):46-58. doi:10.14309/ajg.0000000000002100
- Kim A, et al. Clinicopathologic and Endosonographic Characteristics of Colon Subepithelial Tumors Discovered Incidentally. Diagnostics 2024;14(5):551. doi:10.3390/diagnostics14050551
- Park EY, et al. Feasibility of endoscopic resection and impact of endoscopic ultrasound-based surveillance on colorectal subepithelial tumors. Surg Endosc 2023;37:6867-6876. doi:10.1007/s00464-023-10195-7
- Pal S, Hodgar D. Gastrointestinal Subepithelial Lesions: A Review. J Dig Endosc 2023;14:099-105. doi:10.1055/s-0043-1770923
- Varanese M, et al. Endoscopic Ultrasound and Gastric Sub-Epithelial Lesions. Medicina 2024;60:1695. doi:10.3390/medicina60101695
- Kida M, et al. Endoscopic ultrasonography diagnosis of subepithelial lesions. Dig Endosc 2017;29(4):431-443. doi:10.1111/den.12854
- Jiao J, et al. Efficacy of EUS and endoscopic resection for esophageal schwannoma. Scand J Gastroenterol 2023;58(8):963-969. doi:10.1080/00365521.2023.2185867
- Deprez PH, et al. Endoscopic management of subepithelial lesions including neuroendocrine neoplasms: ESGE Guideline. Endoscopy 2022;54(4):412-429. doi:10.1055/a-1751-5742
- Abulawi AA, et al. Gastrointestinal Subepithelial Lesions: Evolution in Management and Endoscopic Resection Techniques. Curr Gastroenterol Rep 2025;27(1):1. doi:10.1007/s11894-025-00966-8
- Lee JH. Management of Colorectal Subepithelial Lesions. Korean J Gastroenterol 2025;85(3):117-125. doi:10.4166/kjg.2025.004
- Kim T. Colorectal Subepithelial Lesions. Clin Endosc 2015;48(4):302-307. doi:10.5946/ce.2015.48.4.302
- Baysal B, et al. The role of EUS and EUS-guided FNA in esophageal subepithelial lesions. Endosc Ultrasound 2017;6(5):308-316. doi:10.4103/2303-9027.155772
- Li J, et al. Endoscopic ultrasound in precise selection of endoscopic treatment for upper GI submucosal tumors. BMC Surg 2023;23:273. doi:10.1186/s12893-023-02164-7
- Pesenti C, et al. Characterization of subepithelial lesions by contrast-enhanced EUS. Endosc Ultrasound 2018;8(1):43-49. doi:10.4103/eus.eus_89_17
- Vasilakis T, et al. EUS-Guided Diagnosis of Gastric Subepithelial Lesions. Diagnostics 2023;13(13):2176. doi:10.3390/diagnostics13132176
- Kim B, et al. Practice Guidelines for Subepithelial Lesion in Upper GI Endoscopy. J Gastroenterol Hepatol 2026. doi:10.1111/jgh.70225
- Kim SJ. Approach to Gastric Subepithelial Lesions. Korean J Helicobacter Up Gastrointest Res 2025;25(3):209-215. doi:10.7704/kjhugr.2025.0038
- Song GH, et al. Subepithelial lesions of the colon: clinical data and treatment results. Gastrointest Endosc 2018;87(6):AB432. doi:10.1016/j.gie.2018.04.1782
- Shi W, et al. Risk factors for submucosal infiltration of colorectal LSTs. World J Gastrointest Surg 2025;17(8):107230. doi:10.4240/wjgs.v17.i8.107230
- Menon L, Buscaglia JM. Endoscopic approach to subepithelial lesions. Therap Adv Gastroenterol 2014;7(3):123-130. doi:10.1177/1756283x13513538
- Li W, et al. Diagnostic value of EUS for esophageal SELs. Medicine 2024;103(43):e40419. doi:10.1097/md.0000000000040419
- Pimentel-Nunes P, et al. ESD for superficial GI lesions: ESGE Guideline Update 2022. Endoscopy 2022;54(6):591-622. doi:10.1055/a-1811-7025
- Sadeghi A, et al. Management of gastrointestinal SELs. Gastroenterol Hepatol Bed Bench 2023;16(4):378-385. doi:10.22037/ghfbb.v16i4.2690
Have you been diagnosed with a submucosal lesion?
We'll evaluate your case with endoscopic ultrasound and decide together the best plan: monitoring or endoscopic resection.
Book an Appointment