
Peptic Esophagitis: Everything You Need to Know
When stomach acid flows back up again and again, it can end up inflaming and "burning" the esophagus. This is the complete 2026 guide to understand why it happens, when it should be checked and what actually works.

By Dr. Pedro de María Pallarés
Specialist in Gastroenterology
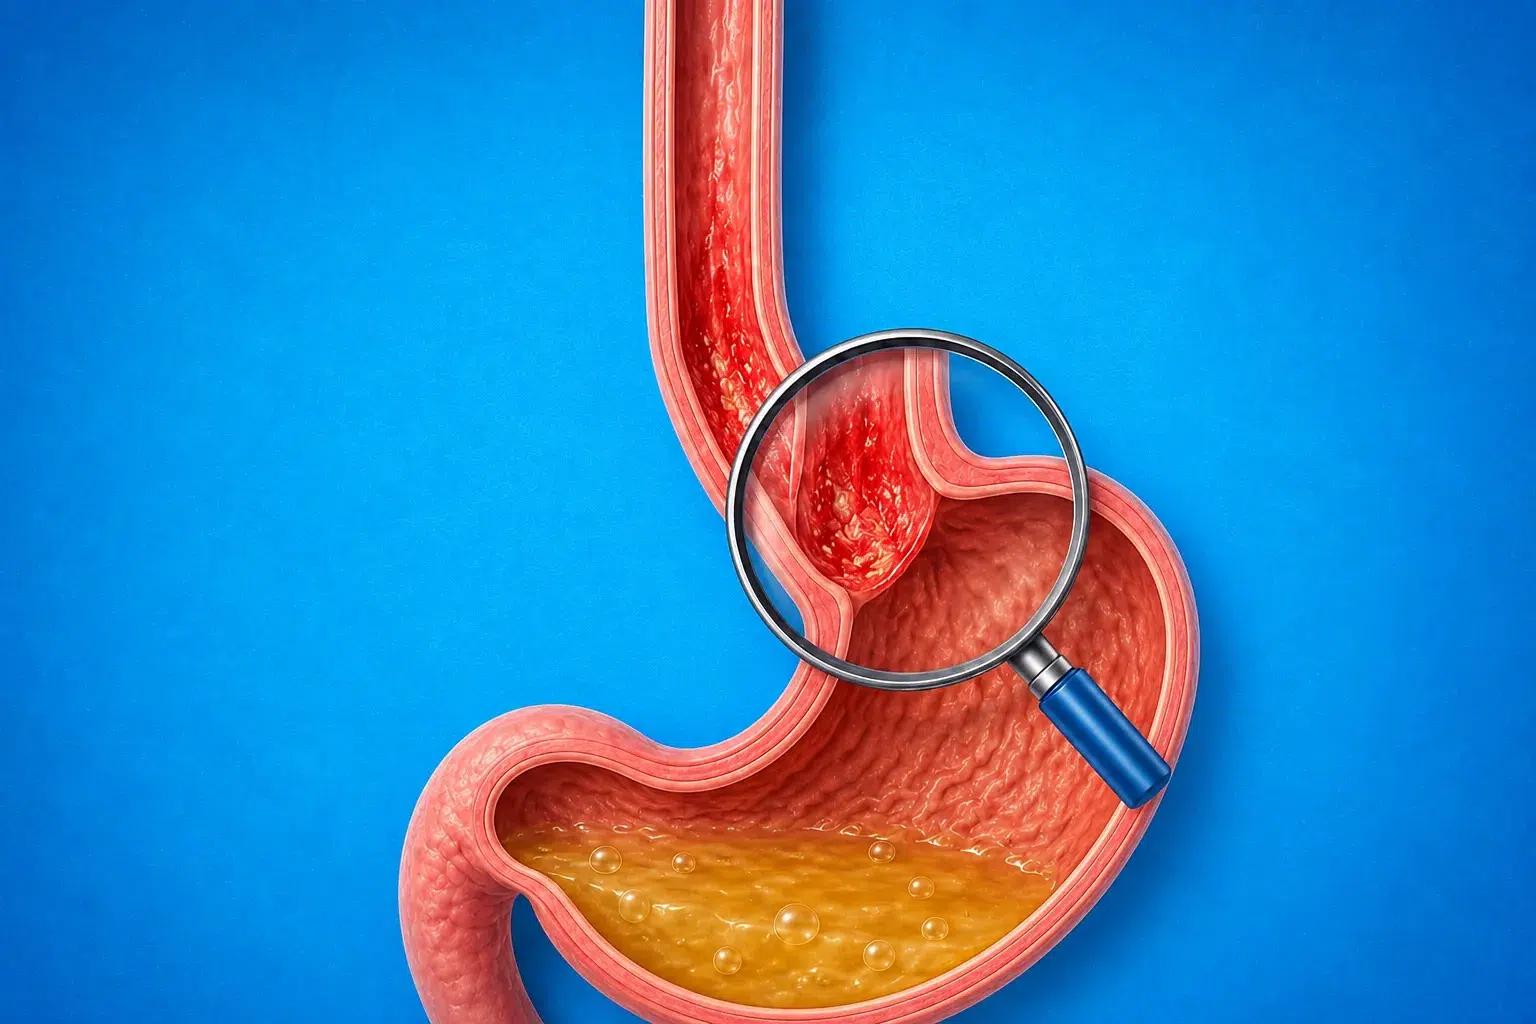
In peptic esophagitis, the acid that flows up from the stomach inflames and erodes the lining of the esophagus.
TL;DR (quick summary)
What is it?
- Inflammation and erosions of the esophagus caused by acid reflux (GERD).
- Graded on endoscopy with the Los Angeles classification (A–D).
What is done?
- Lifestyle changes + PPIs (or the new P-CABs) for ~8 weeks.
- If severe (C/D), repeat the endoscopy to confirm healing and rule out Barrett's.
Is it serious? In most people it heals well and the course is benign; the key is controlling the underlying reflux. Check the warning signs that mean you should not wait.
Peptic esophagitis is inflammation of the esophagus caused by stomach acid that flows back up again and again (reflux). When that acid —together with pepsin, hence "peptic"— stays in contact with the lining for too long, it irritates it until it produces erosions that are visible on endoscopy. In practice it is the "with-injury" form of gastroesophageal reflux disease (GERD), which is why it is also called erosive reflux esophagitis. 1
Quick index
- What is peptic esophagitis?
- Who does it affect? Real numbers
- Causes and risk factors
- Symptoms: how it feels
- Warning signs: when to seek care
- Diagnosis and the Los Angeles classification
- When should the endoscopy be repeated?
- Lifestyle changes that work
- Treatment: PPIs, P-CABs and more
- Complications if left untreated
- My approach in the clinic
- Quick FAQs
- References
What is peptic esophagitis?
The esophagus is the "tube" that carries food from the mouth to the stomach. Unlike the stomach, it is not built to withstand acid. When the valve that separates them (the lower esophageal sphincter) does not close properly, acid flows up, and if it does so repeatedly it eventually inflames the lining. That inflammation with erosions is peptic esophagitis. 1
It is worth distinguishing it from two situations that are often confused: functional heartburn (there is burning but the esophagus is healthy) and eosinophilic esophagitis (inflammation of allergic origin, not caused by acid). That is why, faced with esophagitis, the first step is to confirm that it really is peptic (caused by reflux). 3
Who does it affect? Real numbers
It is very common. A meta-analysis that pooled more than 750,000 people over 26 years estimated a worldwide prevalence of erosive esophagitis (seen on endoscopy) of around 28%, with important variation depending on the region of the world. 16 The good news is that, in most people, the course is benign and the erosions heal with treatment. 13
Causes and risk factors
The underlying cause is almost always gastroesophageal reflux. On top of that, there are factors that clearly increase the risk of erosions appearing:
- Hiatal hernia: the most powerful risk factor (it multiplies the risk by about 4). If you want to understand it well, I have a dedicated guide on hiatal hernia.16
- Obesity, especially abdominal obesity: a large waist circumference increases pressure inside the abdomen and pushes acid upward; abdominal fat matters more than total weight.1617
- Pregnancy: because of hormonal changes and pressure from the uterus, reflux symptoms are far more frequent (up to 4 in 10 pregnant women), especially in the third trimester.18
- Tobacco and alcohol: they relax the valve and favor reflux.
- Some medications and large or late meals, which increase or prolong reflux.
Symptoms: how it feels
The typical symptoms are heartburn (a burning feeling that rises from the stomach toward the chest) and regurgitation (feeling the contents come back up toward the throat or mouth). There may also be chest pain in the center, a sensation of food "getting stuck", coughing or throat clearing. Interestingly, the intensity of the burning does not always match how many erosions there are: there are significant esophagitis cases with few symptoms, and vice versa. 1
Burning, but a healthy esophagus
Not everyone with heartburn has esophagitis. When symptoms are clear but the endoscopy and the acid tests are normal, we call it functional heartburn, which is managed differently. That is why confirming the diagnosis avoids years of mistargeted treatment.
Warning signs: when to seek care without waiting
See a doctor promptly (these symptoms make an endoscopy necessary):1
- Difficulty or pain when swallowing, or a feeling that food gets stuck.
- Unintentional weight loss.
- Persistent vomiting.
- Vomiting blood or black, "tar-like" stools.
- Unexplained anemia or iron deficiency.
Diagnosis and the Los Angeles classification
The test that confirms peptic esophagitis is the upper GI endoscopy (gastroscopy), which lets us see the erosions directly. To describe their severity in a standardized way we use the Los Angeles classification, from A (mild) to D (severe):
| Grade | What is seen on endoscopy |
|---|---|
| A | One or more erosions 5 mm or smaller, not joining between folds. Mild. |
| B | At least one erosion larger than 5 mm, without joining the tops of two folds. |
| C | Erosions that join between folds, but involve less than 75% of the circumference. |
| D | Erosions involving 75% or more of the circumference of the esophagus. Severe. |
This grading matters when deciding treatment and follow-up. According to the Lyon Consensus 2.0 (2024), the current international reference, finding esophagitis of grade B, C or D (or a stricture or Barrett's esophagus) is already considered conclusive evidence of reflux, with no need for further acid testing. 3 That said, telling grade A from grade B is not always easy or reproducible between observers, so an experienced endoscopist's assessment makes the difference. 9
When symptoms persist despite treatment and the endoscopy is normal, the next step is to study the acid with a 24-hour pH-impedance test, which measures how much acid really comes up and whether it relates to the symptoms. 2
When should the endoscopy be repeated?
This is one of the most frequent questions. The answer depends on severity:
- Mild esophagitis (grades A and B): it usually does not need a repeat endoscopy if symptoms improve with treatment.12
- Severe esophagitis (grades C and D): a repeat endoscopy is recommended, while on acid-suppressing treatment, at around 8–12 weeks. It has two goals: confirm that the erosions have healed and rule out Barrett's esophagus that may have been hidden under the inflammation.12
Why rule out Barrett's afterward?
When there are many erosions, Barrett's esophagus can be "covered up". In prospective studies, repeating the endoscopy after healing detected Barrett's in about 12% of patients, and up to around 27% when the initial esophagitis was moderate-to-severe. That is why, in grades C and D, looking again with the lining already healed is important. 1011
A practical detail: biopsies taken when there is still a lot of inflammation are unreliable, so it is best to wait for healing to properly assess the lining. 11 If you are going to have a gastroscopy, here I explain what the gastroscopy preparation is like.
Lifestyle changes that work
There are a lot of myths here. Looking closely at the evidence, only a few measures have objectively been shown to reduce acid in the esophagus or symptoms. These are the ones really worth it:
- Lose weight if overweight: the measure with the best evidence. Weight loss proportionally reduces acid exposure and symptoms.1415
- Raise the head of the bed (not just more pillows: lift the head of the bed by about 15–20 cm) and, if you can, sleep on your left side.14
- Do not eat in the 2–3 hours before lying down: going to bed with a full stomach multiplies nighttime reflux.15
- Quit smoking: it reduces reflux symptoms, especially in people who are not overweight.15
- Avoid your personal triggers (many people are bothered by alcohol, coffee, chocolate, fried or spicy food): cutting these out across the board does not work for everyone, but removing the ones that trigger your symptoms does help with comfort.14
You will find more practical advice in my post with heartburn tips you don't know.
Treatment: PPIs, P-CABs and more
The goal is twofold: that the erosions heal and that they stop appearing. Treatment combines the lifestyle changes above with medications that reduce acid.
1. Proton pump inhibitors (PPIs)
PPIs (omeprazole, esomeprazole, pantoprazole, etc.) are the treatment of choice and heal esophagitis better than the older H2-blocker antacids. The usual schedule is one dose a day for 8 weeks. A detail many patients are unaware of: the PPI works better if taken 30–60 minutes before a meal, not at bedtime. 1
Once healed, in many people the dose can be stepped down to the lowest effective dose and reviewed periodically to see whether it is still needed. And no: taking PPIs for the indicated time and under control is safe; I explain it in detail in does omeprazole cause cancer?. 2
2. The new P-CABs (vonoprazan)
Potassium-competitive acid blockers (P-CABs), such as vonoprazan, are the novelty of recent years. They block acid more quickly and steadily than PPIs and, in addition, do not depend on being taken before meals. The FDA approved vonoprazan for erosive esophagitis in November 2023. 5
In the pivotal trial, vonoprazan healed esophagitis at least as well as lansoprazole, with an especially clear advantage in severe (grades C and D) esophagitis. 4 Its maintenance use has been studied for up to 5 years with a safety profile similar to that of PPIs. 6 That is why it is an option to consider especially in the most severe esophagitis or in cases that do not heal well with PPIs.
3. When symptoms don't settle
If discomfort persists despite treatment, the first step is to check that the diagnosis is correct and that the medication is being taken properly; many cases labeled "refractory" actually are not. The strategy is to optimize the dosing, consider switching to a P-CAB and, if true resistant reflux is confirmed, study it with pH-impedance and consider add-on options (alginates, neuromodulators) or, in selected cases, anti-reflux surgery, closely tied to the treatment of hiatal hernia. 78
A point from the most recent guidelines: in someone already on 8 weeks of twice-daily PPI without response, it usually makes no sense to keep increasing the dose; it is better to reassess the diagnosis. 8 You can see more related topics in my gastrointestinal disorders area.
Complications if left untreated
Most cases of peptic esophagitis do well, but if reflux remains uncontrolled for years it can cause problems:
- Peptic stricture: the esophagus narrows due to scarring and swallowing becomes difficult.
- Barrett's esophagus: the lining changes to protect itself from acid; it carries a small increase in cancer risk and requires surveillance. I explain it in the cancer risk of Barrett's esophagus.
- Ulcers and bleeding, which can cause anemia.
Precisely to avoid these situations it makes sense to confirm the diagnosis, treat properly and check again when appropriate. 1
My approach in the clinic
Many people arrive after years of taking antacids on demand, without a clear diagnosis. My priority is to confirm whether the esophagitis is really peptic with a well-performed endoscopy, grade it with the Los Angeles classification and, depending on severity, decide whether the test should be repeated to rule out Barrett's.
From there, I build a tailored plan: the lifestyle measures that really work, the right medication (a PPI or, in selected cases, a P-CAB) and the lowest dose needed to keep the esophagus healthy. If reflux is resistant or there is a large hiatal hernia, we weigh the options together. You can learn about my work in advanced endoscopy.
If you have had heartburn, regurgitation or difficulty swallowing for a while, we can study your case in depth.
Related reading (to complete the picture)



A personal touch (yes, this is medicine too)
Behind every case of esophagitis there is a person tired of living with the burning and of not knowing whether it is "something serious". My commitment is to confirm what is going on, explain it calmly and give a clear plan: from lifestyle to advanced endoscopy when needed.

FAQ: quick questions about peptic esophagitis
What is the difference between peptic esophagitis and reflux (GERD)?
Reflux (GERD) means that acidic stomach contents flow back up into the esophagus. Peptic esophagitis is one of its consequences: when that acid damages and inflames the wall of the esophagus and erosions appear that are visible on endoscopy. 1
Can peptic esophagitis be cured?
Yes. With acid-suppressing treatment (PPIs or, now, the new P-CABs) and lifestyle changes, the erosions heal in most cases within about 8 weeks. What usually needs long-term control is the underlying reflux. 4
When should the endoscopy be repeated in peptic esophagitis?
In mild esophagitis (grades A and B) it usually is not needed. In severe esophagitis (grades C and D) a repeat is recommended, while on treatment, to confirm healing and rule out a Barrett's esophagus that might be hidden. 12
Which lifestyle changes really help?
Losing weight if overweight, raising the head of the bed, not eating in the 2–3 hours before lying down, sleeping on the left side and quitting smoking. Avoiding your trigger foods helps with comfort. 14
References (clickable)
- Katz PO, Dunbar KB, Schnoll-Sussman FH, et al. ACG Clinical Guideline for the Diagnosis and Management of Gastroesophageal Reflux Disease. Am J Gastroenterol (2022). PMID: 34807007 (opens in a new tab)
- Yadlapati R, Gyawali CP, Pandolfino JE, et al. AGA Clinical Practice Update on the Personalized Approach to the Evaluation and Management of GERD. Clin Gastroenterol Hepatol (2022). Full text (PMC) (opens in a new tab)
- Gyawali CP, Yadlapati R, Fass R, et al. Updates to the modern diagnosis of GERD: Lyon consensus 2.0. Gut (2024). PMID: 37734911 (opens in a new tab)
- Laine L, DeVault K, Katz P, et al. Vonoprazan Versus Lansoprazole for Healing and Maintenance of Healing of Erosive Esophagitis: A Randomized Trial. Gastroenterology (2023). PMID: 36228734 (opens in a new tab)
- Hossa K, Małecka-Wojciesko E. Advances in GERD Management: the Role of Potassium-Competitive Acid Blockers and Novel Therapies. Pharmaceuticals (Basel) (2025). Full text (PMC) (opens in a new tab)
- Uemura N, Kinoshita Y, Haruma K, et al. Vonoprazan as a Long-term Maintenance Treatment for Erosive Esophagitis: VISION, a 5-Year, Randomized, Open-label Study. Clin Gastroenterol Hepatol (2024). PMID: 39209187 (opens in a new tab)
- Davis TA, Gyawali CP. Refractory Gastroesophageal Reflux Disease: Diagnosis and Management. J Neurogastroenterol Motil (2024). PMID: 38173155 (opens in a new tab)
- Armstrong D, Hungin AP, Kahrilas PJ, et al. Management of PPI-refractory reflux-like symptoms: international working group consensus. Aliment Pharmacol Ther (2025). PMID: 39740235 (opens in a new tab)
- Spechler SJ, Laine L, DeVault KR, et al. Comparison of Los Angeles Grades of Erosive Esophagitis Scored by Local Investigators vs Central Adjudicators. Clin Gastroenterol Hepatol (2024). PMID: 38777170 (opens in a new tab)
- Hanna S, Rastogi A, Weston AP, et al. Detection of Barrett's esophagus after endoscopic healing of erosive esophagitis. Am J Gastroenterol (2006). PMID: 16863541 (opens in a new tab)
- Gilani N, Gerkin RD, Ramirez FC, et al. Prevalence of Barrett's esophagus in patients with moderate to severe erosive esophagitis. World J Gastroenterol (2008). Full text (PMC) (opens in a new tab)
- Pandolfino JE, Spechler SJ, Yadlapati R. Updates in the Management of Erosive Esophagitis. J Fam Pract (2023). Full text (PMC) (opens in a new tab)
- Bi D, Katzka DA, Lavey CJ, et al. Erosive Esophagitis Portends a Benign Clinical Course in the Majority of Patients. Dig Dis Sci (2020). PMID: 31907769 (opens in a new tab)
- Kaltenbach T, Crockett S, Gerson LB. Are lifestyle measures effective in patients with GERD? An evidence-based approach. Arch Intern Med (2006). PMID: 16682569 (opens in a new tab)
- Ness-Jensen E, Hveem K, El-Serag H, Lagergren J. Lifestyle Intervention in Gastroesophageal Reflux Disease. Clin Gastroenterol Hepatol (2016). Full text (PMC) (opens in a new tab)
- Witarto AP, Witarto BS, Pramudito SL, et al. Risk factors and 26-years worldwide prevalence of endoscopic erosive esophagitis: a meta-analysis. Sci Rep (2023). Full text (PMC) (opens in a new tab)
- Koo JS, Lee SW, Park SM, et al. Abdominal obesity as a risk factor for the development of erosive esophagitis. Gut Liver (2009). Full text (PMC) (opens in a new tab)
- Khurmatullina AR, Andreev DN, Maev IV, et al. Global prevalence and risk of GERD symptoms in pregnancy: a meta-analysis. BMC Pregnancy Childbirth (2025). Full text (PMC) (opens in a new tab)
Heartburn that won't go away? Let's check your esophagus
We confirm whether there is esophagitis, grade it and design a clear plan —from lifestyle to the right treatment—.
Book my assessment
Transparency: this article is not sponsored by any pharmaceutical company; the recommendations are based on the cited evidence.