
Pharyngeal Globus: What Is That Sensation You Feel in Your Throat?
That feeling of a "lump", knot or foreign body in the throat that won't go away —but that doesn't bother you when you eat— has a name. This is the updated 2026 guide to understand why it happens and when it should be checked.

By Dr. Pedro de María Pallarés
Specialist in Gastroenterology
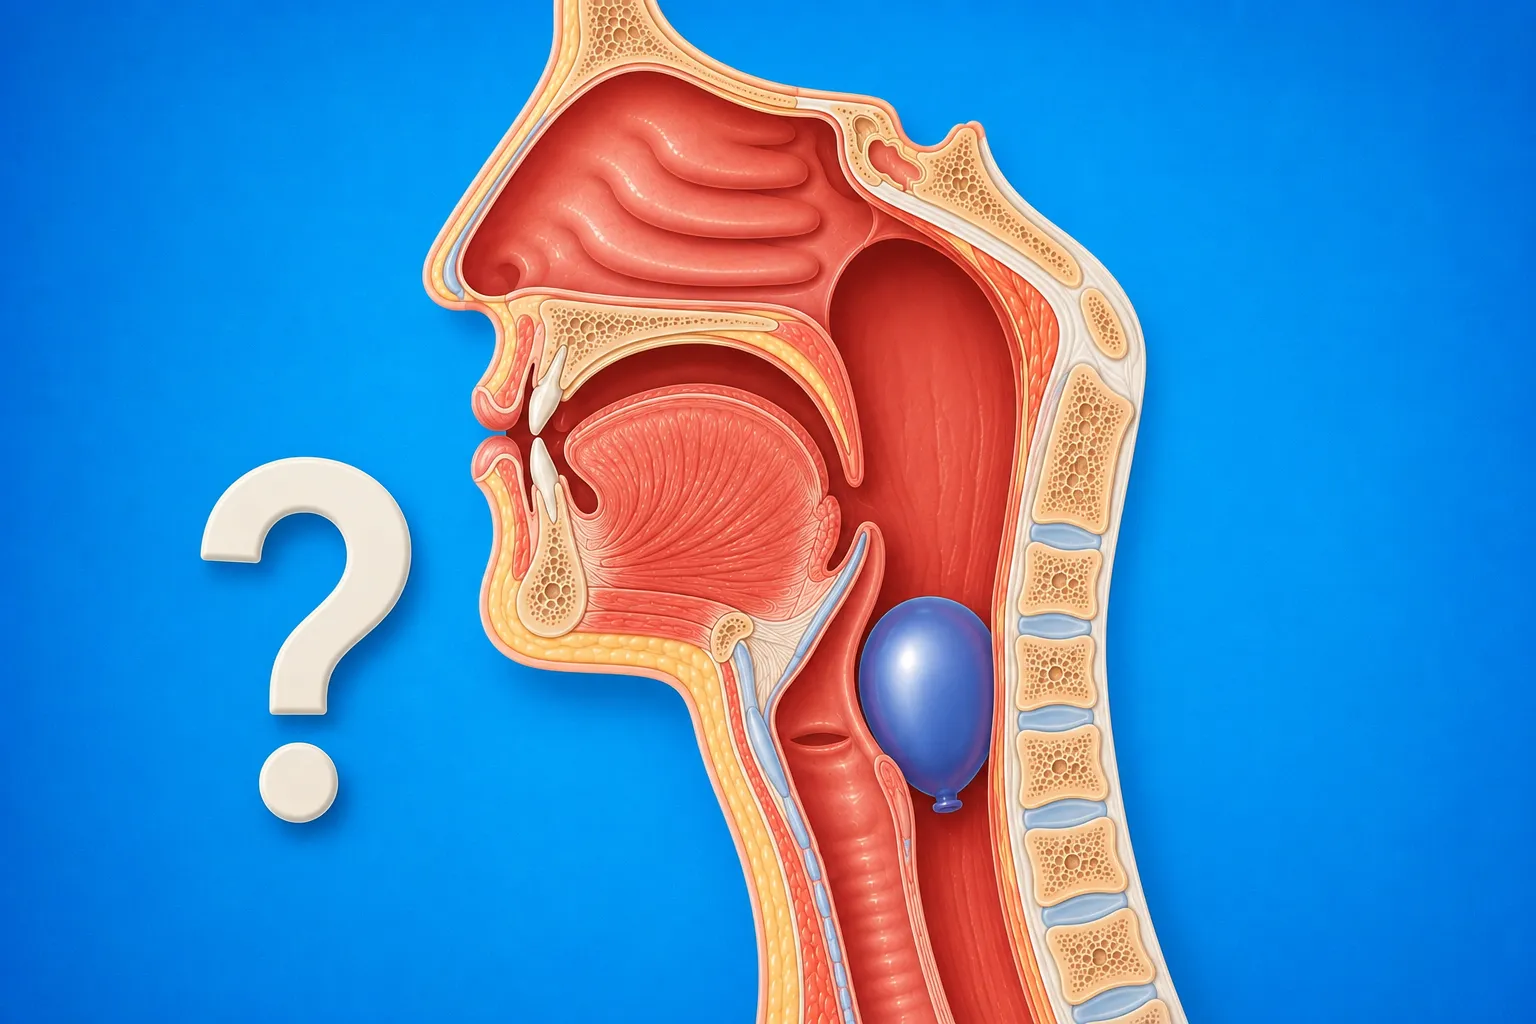
In pharyngeal globus you feel a "lump" in the throat, even though there is nothing there when it is examined.
TL;DR (quick summary)
What is it?
- A sensation of a lump or foreign body in the throat, painless and usually better when eating.
- It is a functional disorder (of the gut–brain connection), almost never serious.
What is done?
- Reassuring explanation + treating reflux only if present.
- Speech therapy, cognitive behavioral therapy and, if needed, neuromodulators.
Is it dangerous? Almost never: in most cases there is nothing malignant. But check the warning signs that mean you should not wait.
Pharyngeal globus is the persistent or intermittent, painless sensation of having a lump, knot or foreign body in the throat without anything actually being there to explain it. It is very characteristic that it does not bother you —or even improves— when you eat and that it causes no true difficulty swallowing. Today we understand it as a functional disorder of the gut-brain interaction, not as a serious structural disease. 13
Quick index
What is pharyngeal globus?
"Pharyngeal globus" (globus pharyngeus) is the medical term for that feeling of having something in the throat —a knot, a ball, a lump— that does not correspond to any real object. For years it was unfairly called "globus hystericus", but that idea is completely outdated: today we know it has a real physical and nervous basis and is not something "imaginary". 4
It is part of the functional esophageal disorders (now called disorders of gut–brain interaction) of the international Rome criteria, alongside functional heartburn or functional chest pain. These criteria were updated in 2026 to their 5th edition (Rome V), which keeps globus within this group. In simple terms: the digestive tract and the nerves that control it work in a somewhat "hypersensitive" way, so the body notices discomfort in an area that is actually healthy. 1217
Is it common? Is it dangerous?
It is very common: it is estimated that up to 46% of people have felt this sensation at some point in their lives, and it accounts for around 4% of first visits to ENT (Otolaryngology). It appears especially in middle age and women consult more often. 3
A reassuring message
The most common fear is that it is cancer. In a study of 122 patients with globus, 84% had anxiety for that reason, but after the examination no malignant lesion was found and nearly 95% were reassured simply by the specialist's assessment. In other words: in the vast majority of cases, pharyngeal globus is bothersome but benign. 6
Why does it appear? Causes
The cause is almost never single: it is usually multifactorial. These are the mechanisms that recur most: 5
- Reflux, acid or laryngopharyngeal: it irritates the throat and esophagus area. It is documented in some patients, although —note— it also appears in people without symptoms, so it is not always the culprit. To go deeper, see my guides on gastroesophageal reflux and peptic esophagitis.3
- Excess tension in the muscle at the entrance of the esophagus (the upper esophageal sphincter): in people with globus, the resting pressure of that muscle is elevated far more often than in those without it (around 28% versus 3%).7
- Mild motility changes in the esophagus, present in about half of patients.7
- Hypersensitivity and psychological factors: anxiety and stress are closely related to globus. In fact, in those with a more tense entrance muscle, anxiety is far more prevalent, with a strong correlation between tension and anxiety.9
There are less frequent causes (thyroid problems, cervical spine osteophytes, tissue remnants…), but they are the exception. The key idea is that in a good number of cases there is no demonstrable reflux, and that explains why antacids do not always work. 37
How it feels (and how it doesn't)
Pharyngeal globus is fairly recognizable. The typical pattern is:
- A sensation of a lump, knot, tightness or "hair/crumb" in the midline of the neck, at throat level.
- It does not hurt and, very characteristically, does not worsen —or even improves— when swallowing food or liquids.
- It tends to be felt more when swallowing saliva "dry" or during stress.
By definition, globus does not include true difficulty swallowing (dysphagia) or pain on swallowing (odynophagia). If they appear, it no longer fits a simple globus and requires investigation. That difference is precisely what draws the line between what is benign and what should be checked. 25
Warning signs: when to seek care without waiting
It is not a "simple" globus and you should be assessed soon (probably with an ENT examination or an endoscopy) if you notice:1011
- Difficulty swallowing (especially if it is getting worse) or pain on swallowing.
- Unintentional weight loss.
- Hoarseness or voice changes lasting more than 3 weeks.
- A lump in the neck.
- That the sensation is only on one side (lateralized) or progressively worsening.
- Greater vigilance if you are 45 or older with a history of tobacco or alcohol.
How is it diagnosed?
Pharyngeal globus is a clinical diagnosis: it is based mainly on a good history and on examination of the throat (laryngoscopy) by the specialist. It is not an "endless exclusion" diagnosis: when the picture is typical and there are no warning signs, no endless tests are needed. 12
When there are doubts or red flags, the most helpful tests are upper GI endoscopy (to look at the esophagus and rule out inflammation, eosinophilic esophagitis or other causes) and, in selected cases, pH-impedance and esophageal manometry to study reflux and motility. Here I explain the gastroscopy preparation. 5
Treatment: what works
The treatment of globus has changed quite a bit, and it is worth sorting out what really helps:
1. Explanation and reassurance (the cornerstone)
It may seem like little, but it is the most effective thing: understanding what it is, why it happens and that it is not cancer reduces anxiety —and, with it, the sensation itself—. In studies, the specialist's assessment reassures the vast majority of patients. 612
2. Treat reflux… only if it is present
The omeprazole-for-globus myth
Overall, proton pump inhibitors (omeprazole and similar) have not been shown to work better than placebo for globus. They only help the subgroup that actually has reflux (with heartburn or regurgitation) and short-duration symptoms. That is why it makes no sense to take antacids indefinitely "just in case". 813
3. Speech therapy and cognitive behavioral therapy
Since many cases involve excess tension in the throat muscles and an anxiety component, two very useful approaches are speech/voice therapy (exercises to relax the area, breathing, stopping throat-clearing) and cognitive behavioral therapy. In fact, a recent trial found that both CBT-based psychoeducation and neuromodulators improved symptoms more than omeprazole. 1415
4. Neuromodulators in resistant cases
When globus persists despite the above, low-dose medications that "calm" the nervous hypersensitivity —such as gabapentin or amitriptyline— can help. In one series, two out of three patients who did not improve with anti-reflux treatment did improve when gabapentin was added. 16
If the throat sensation is accompanied by sudden episodes of nighttime choking, you may be interested in my post on glottic spasm. And you can find more topics in my gastrointestinal disorders area and on functional digestive disorders.
My approach in the clinic
Many people come to the clinic frightened, convinced that the "lump" is something bad. My first task is usually twofold: rule out anything important with a good examination and, when needed, an endoscopy; and, above all, explain calmly what is going on, because understanding it already relieves much of the symptom.
From there, I look for the specific cause: if there is reflux, we treat it; if tension and anxiety predominate, I steer toward speech therapy or cognitive behavioral therapy; and if the globus is resistant, we consider a neuromodulator. The key is not to chronify treatments that add nothing (such as taking omeprazole for years without reflux) and to support each patient until the throat stops sending that signal.
If you have had that lump sensation in your throat for a while, we can study your case and remove the uncertainty.
Related reading (to complete the picture)


A personal touch (yes, this is medicine too)
Behind every "I have something in my throat" there is a person who has been worrying about it for weeks and fearing the worst. My commitment is to look carefully to rule out anything important and then give peace of mind with an honest explanation and a clear plan.

FAQ: quick questions about pharyngeal globus
What is pharyngeal globus?
It is the persistent or intermittent, painless sensation of having a lump or foreign body in the throat without anything actually being there. It usually improves with eating and does not cause real difficulty swallowing. It is a functional disorder, not a serious disease. 2
Is pharyngeal globus a sign of cancer?
Almost never. In studies, the vast majority of patients with globus have no malignant lesion. You should see a doctor sooner if there is difficulty or pain swallowing, weight loss, persistent hoarseness, a neck lump or if the symptoms are only on one side. 6
Why does that lump sensation in the throat appear?
It is usually multifactorial: reflux, excess tension in the muscle at the entrance of the esophagus, mild motility changes and, very often, hypersensitivity and anxiety. In many cases there is no demonstrable reflux. 7
Does omeprazole cure pharyngeal globus?
It only helps if there really is reflux behind it. Overall, PPIs do not work better than placebo for globus. When there is no reflux, reassuring explanation, speech therapy, cognitive behavioral therapy and, if needed, neuromodulators such as gabapentin are more useful. 8
References (clickable)
- Aziz Q, Fass R, Gyawali CP, et al. Functional Esophageal Disorders. Gastroenterology (2016). PMID: 27144625 (opens in a new tab)
- The Rome Foundation. Rome IV Diagnostic Criteria for Disorders of Gut-Brain Interaction (A4. Globus) (2016). Rome IV criteria (opens in a new tab)
- Lee BE, Kim GH. Globus pharyngeus: a review of its etiology, diagnosis and treatment. World J Gastroenterol (2012). Full text (PMC) (opens in a new tab)
- Järvenpää P, Arkkila P, Aaltonen LM. Globus pharyngeus: a review of etiology, diagnostics, and treatment. Eur Arch Otorhinolaryngol (2018). PMID: 29943257 (opens in a new tab)
- Zerbib F, Rommel N, Pandolfino J, Gyawali CP. Diagnosis and management of globus sensation: a clinical challenge (ESNM/ANMS Review). Neurogastroenterol Motil (2020). PMID: 32329203 (opens in a new tab)
- Rasmussen ER, Schnack DT, Ravn AT. A prospective cohort study of 122 adult patients presenting with globus pharyngeus. Clin Otolaryngol (2018). PMID: 29327493 (opens in a new tab)
- Manabe N, Tsutsui H, Kusunoki H, et al. Pathophysiology and treatment of patients with globus sensation — esophageal motility dysfunction. J Smooth Muscle Res (2014). PMID: 26081369 (opens in a new tab)
- Harvey PR, Theron BT, Trudgill NJ. Managing a patient with globus pharyngeus. Frontline Gastroenterol (2018). PMID: 30046425 (opens in a new tab)
- Lan QL, Lin XX, Wang Y, et al. The Relationship Between Upper Esophageal Sphincter Pressure and Psychological Status in Patients with Globus Sensation. Int J Gen Med (2021). PMID: 34858048 (opens in a new tab)
- National Institute for Health and Care Excellence (NICE). Suspected cancer: recognition and referral. NICE guideline [NG12] (2015). NG12 guideline (opens in a new tab)
- University of Iowa, Department of Otolaryngology. Lump in Throat / Globus Sensation. Iowa Head and Neck Protocols (2019). ENT protocol (opens in a new tab)
- Karkos PD, Wilson JA. The diagnosis and management of globus pharyngeus: our perspective from the United Kingdom. Curr Opin Otolaryngol Head Neck Surg (2008). PMID: 19005323 (opens in a new tab)
- Jeon HK, Kim GH, Choi MK, et al. Clinical Predictors for Response to Proton Pump Inhibitor Treatment in Patients With Globus. J Neurogastroenterol Motil (2013). doi:10.5056/jnm.2013.19.1.47 (opens in a new tab)
- Poovipirom N, Ratta-Apha W, Maneerattanaporn M, et al. Treatment outcomes in patients with globus: a randomized control trial of psychoeducation, neuromodulators, and proton pump inhibitors. Neurogastroenterol Motil (2023). PMID: 36443929 (opens in a new tab)
- Ruckart KW, McKone M, Phillips JG, et al. Efficacy of Speech-Language Pathology Interventions for Globus Pharyngeus: A Scoping Review. J Voice (2024). doi:10.1016/j.jvoice.2024.02.027 (opens in a new tab)
- Kirch S, Gegg R, Johns MM, Rubin AD. Globus pharyngeus: effectiveness of treatment with proton pump inhibitors and gabapentin. Ann Otol Rhinol Laryngol (2013). doi:10.1177/000348941312200803 (opens in a new tab)
- Drossman DA, Chang L, Tack J. Disorders of Gut-Brain Interaction and the Rome V Process. Gastroenterology (2026). PMID: 42031435 (opens in a new tab)
Had a "lump" in your throat for a while? Let's clear up the doubt
I examine you, we rule out anything important and I explain calmly what is going on and which plan fits you.
Book my assessment
Transparency: this article is not sponsored by any pharmaceutical company; the recommendations are based on the cited evidence.