
Making sense of your labs · Iron & ferritin
High ferritin: when to suspect (or rule out) hemochromatosis
Most high ferritins aren't hemochromatosis. Step by step, I'll explain what your result means, when there is genuine cause for concern, and why a single test — transferrin saturation — changes everything.
 Dr. Pedro de María · Gastroenterology
July 4, 2026
~14 min read
11 references (PubMed, ACG & EASL guidelines)
Having high ferritin almost never means hemochromatosis: 9 out of 10 high ferritins aren't due to excess iron, but to fatty liver, metabolic syndrome, alcohol or inflammation. Ferritin is an acute-phase reactant: it rises for many reasons that have nothing to do with iron.
The test that sorts it out is transferrin saturation. If it's normal, it's almost always a harmless cause and no genetic testing is needed. If it's high (above 45-50%), then hemochromatosis does need ruling out with a genetic test. And even if it's confirmed, treated early it has an excellent outlook.
~90%
of high ferritins are not iron overload
>45-50%
transferrin saturation: the threshold that raises suspicion
28% / 1%
C282Y homozygotes (♂/♀) who develop iron-related disease
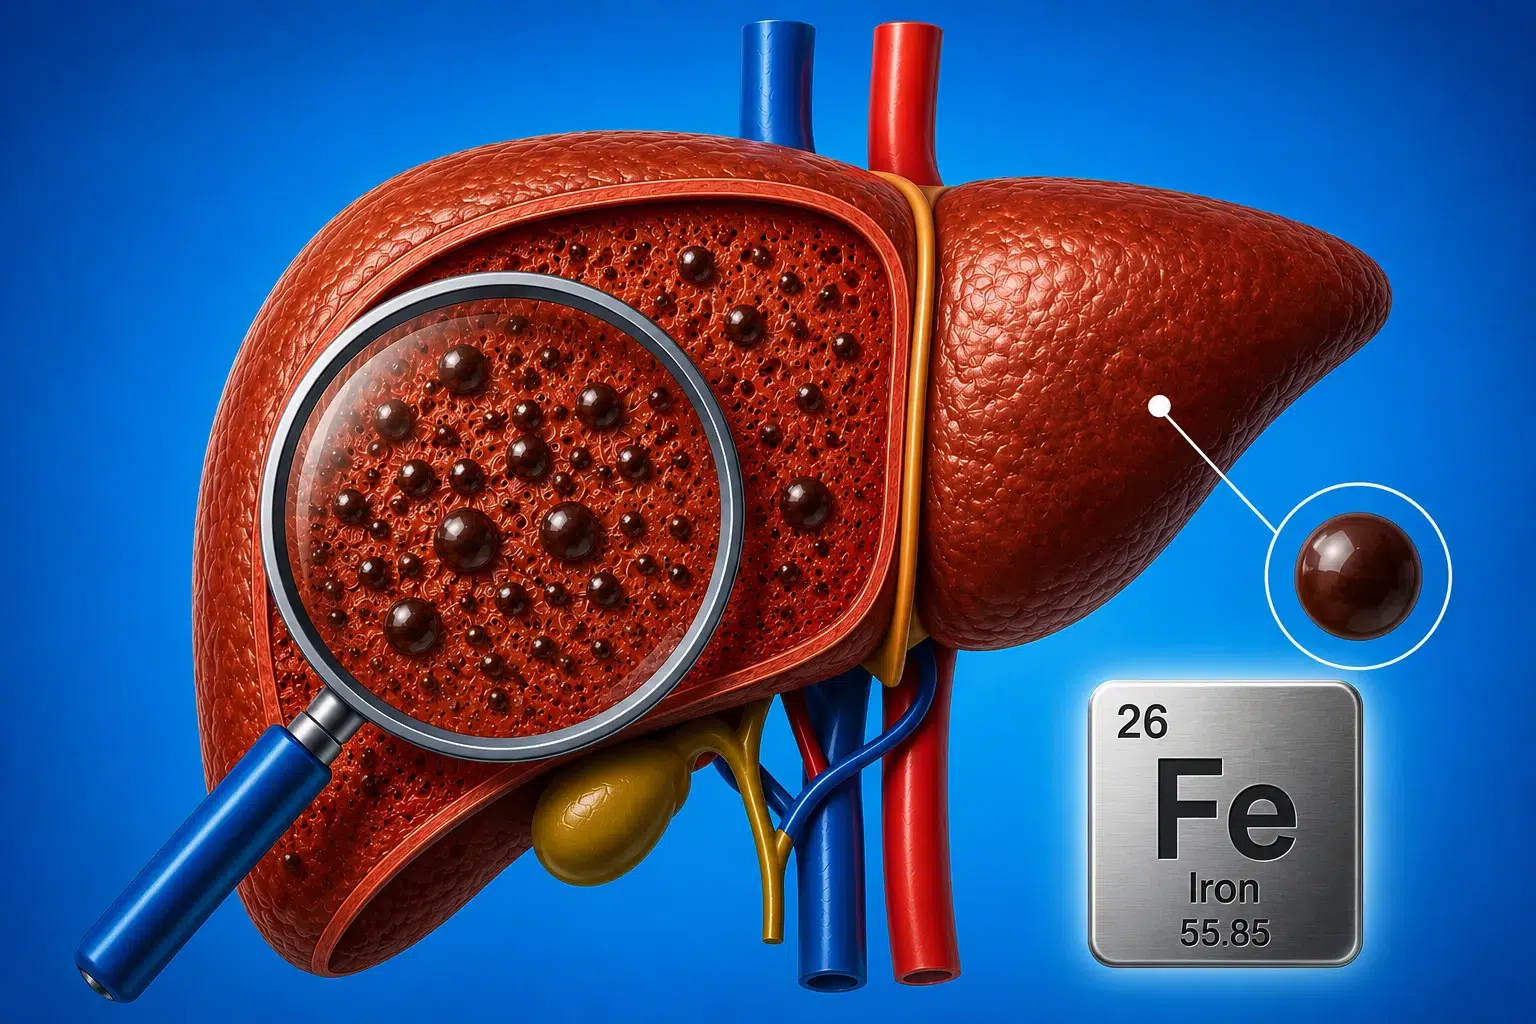
Informational guide: it does not replace your doctor's assessment. If you have questions about your blood test, discuss them with a healthcare professional.
A high ferritin is one of those blood-test findings that sets off alarm bells: you search online, the word "hemochromatosis" pops up, and panic sets in. The reality is far more reassuring. In the vast majority of cases the explanation is simple and benign, and to know whether you need to worry it's almost always enough to look at one more number. Let's take it step by step.
1Part 1 of 8
What ferritin is (and why a high number isn't the same as "too much iron")
Ferritin is the protein that stores iron inside cells, mostly in the liver. That's why, under normal conditions, its level in the blood reflects how much iron you have in store. The catch is that ferritin is also an acute-phase reactant: it shoots up with almost any inflammation, it's released from liver cells when they're damaged, and it rises with alcohol or metabolic syndrome. So a high ferritin can mean excess iron… or none of those things. 12
At what number is it considered high? As a guide, levels above 300 µg/L in men and post-menopausal women, and above 200 µg/L in women before menopause, are regarded as elevated. Every lab has its own range, so what matters isn't the exact decimal, but the context. 1
First, some reassurance
Around 90% of people with high ferritin do not have iron overload. Put another way: in clinical practice, only about 1 in 10 cases of high ferritin corresponds to a real excess of iron. The high number, on its own, is almost never the problem. 13
Key point: ferritin doesn't only measure iron. A high number is the start of the story, not the end.
2Part 2 of 8
Why most high ferritins are NOT hemochromatosis
If most high ferritins aren't an excess of iron, what are they? In the great majority, ferritin rises as a reflection of some other underlying situation. By far the most common causes are these: 14
- Metabolic syndrome and fatty liver: this is the most common cause of a moderately high ferritin. It's called "dysmetabolic hyperferritinemia" and goes hand in hand with excess weight, insulin resistance, high cholesterol and blood pressure.
- Alcohol: heavy drinking raises ferritin in its own right, even without iron overload.
- Inflammation and infections: any inflammatory process, acute or chronic, pushes it up. It's the same thing that raises C-reactive protein.
- Liver damage: when liver cells are injured (by viruses, fat or medications), they release ferritin into the blood.
- Kidney disease and some tumors: less common causes, but possible.
The most telling fact: up to a third of people with fatty liver and metabolic syndrome have somewhat increased iron stores, and even so their transferrin saturation is usually normal. That's why, faced with a high ferritin, it makes no sense to assume the rare thing (a genetic disease) before ruling out the common ones (a fatty liver or some extra weight). 3
3Part 3 of 8
The test that changes everything: transferrin saturation
Here's the key to the whole article. Faced with a high ferritin, the test that really decides is transferrin saturation (also called TSAT). Transferrin is the "truck" that carries iron around the blood; the saturation measures what percentage of those trucks are loaded. It's the preferred initial test and is measured, ideally, while fasting. 5
What matters for you, in two sentences: a normal transferrin saturation, alongside a ferritin that isn't extreme, all but rules out iron overload (it has a 97% negative predictive value) and points to a harmless cause. In contrast, a saturation above 45% identifies almost every patient with classic hemochromatosis (98-100% of C282Y homozygotes) and means the workup should continue. 5
The thresholds we use (European EASL 2022 guideline)
Iron overload should be ruled out when ferritin and saturation are both high:
- In men and post-menopausal women: saturation > 50% and ferritin > 300 µg/L.
- In women before menopause: saturation > 45% and ferritin > 200 µg/L.
If saturation is normal, the high ferritin is almost always reactive (metabolic, alcohol, inflammation) and no genetic test is needed up front. 2
Key point: high ferritin + normal saturation = reassurance. High ferritin + high saturation = it needs looking into.
4Part 4 of 8
Hereditary hemochromatosis: what it is and why not everyone develops it
Classic hereditary hemochromatosis is a change in the HFE gene: those who have it absorb more iron than they need over the years, and that iron gradually builds up in the liver, pancreas, heart and joints. The most common form occurs in people with two copies of the C282Y mutation (being a "homozygote"), and it's especially frequent in people of Northern European ancestry: around 1 in 150-230 people of that background. 267
And here comes the most important — and most reassuring — nuance: having the gene is not the same as having the disease. This is called "incomplete penetrance". A great many people with two copies of C282Y never accumulate enough iron to become ill in their whole lives. 8
Having the gene isn't having the disease
In a study that followed C282Y homozygotes for ~12 years, only 28% of men and 1% of women developed documented iron-overload disease. 8 The European guidelines sum it up like this: up to 38-50% may go on to accumulate iron, but only 10-33% develop any problem attributable to the disease. Women, thanks to menstrual blood loss, are far more protected. 2
5Part 5 of 8
When to really suspect hemochromatosis (and when not)
When hemochromatosis does start to show itself, its first symptoms are non-specific and easy to mistake: mainly fatigue and joint pain. A typical detail is pain in the knuckles of the second and third fingers (the joints you squeeze when shaking hands). Later on, diabetes, erectile dysfunction or liver problems can appear. 9
The sensible way to read your blood test is to cross-check ferritin with transferrin saturation and with your own context. This table sums up which way each scenario points:
| Points more to hemochromatosis | Points more to a reactive cause (the most common) |
|---|---|
| Transferrin saturation high (> 45-50%) | Transferrin saturation normal |
| Fatigue, knuckle pain, unexplained diabetes or impotence | Overweight, fatty liver, high cholesterol or blood sugar |
| First-degree relative with hemochromatosis | High alcohol intake |
| Northern European ancestry | Recent infection or inflammation |
If your case fits the right-hand column — which is the most usual — the path is generally to treat the underlying cause (lose weight, look after your fatty liver, cut down on alcohol) and repeat the blood test. It's the same logic as other findings that are alarming but rarely serious, such as a high bilirubin from Gilbert's syndrome or a high amylase from macroamylasemia. 23
6Part 6 of 8
How it's confirmed: genetics, MRI and (sometimes) biopsy
When ferritin and transferrin saturation are both high, the next step is the HFE genetic test (which looks for the C282Y and H63D mutations). It's a simple blood test and a standard part of the workup when iron studies are elevated; it's not indicated for any isolated high ferritin. 5
To find out how much iron is actually stored in the liver, today we use an MRI scan (with T2*/R2 sequences, the basis of FerriScan). It measures liver iron non-invasively and precisely, and has eliminated the need for a biopsy in most patients. 510
A liver biopsy is reserved for specific cases: mainly to assess whether there is already fibrosis or cirrhosis when ferritin is very high. A useful figure: a ferritin below 1000 µg/L at diagnosis identifies patients at low risk of advanced liver damage; the risk rises clearly above that number, and that's where a biopsy is considered. 5
7Part 7 of 8
What iron does if left untreated
It's worth being clear about this, without scaremongering: hemochromatosis matters when iron has been building up for years and no one has stopped it. In that situation, iron can damage several organs: 92
- Liver: fibrosis and cirrhosis; once there is cirrhosis, the risk of liver cancer rises.
- Pancreas and skin: the classic "bronze diabetes" (diabetes from iron deposits plus darker skin; the pigmentation appears in about 70% of advanced cases).
- Heart: cardiomyopathy and arrhythmias.
- Hormones: hypogonadism, with erectile dysfunction or loss of libido.
- Joints: arthropathy that can persist even after the iron is removed.
The good news is that this scenario is avoidable: the whole point is to detect and stop the iron before any of this happens. That's why the goal isn't to panic over a high ferritin, but to look into it properly and in good time.
8Part 8 of 8
Treatment and outlook: phlebotomy
The treatment for hemochromatosis with iron overload is surprisingly simple and very effective: phlebotomy, that is, removing blood on a regular basis, just like a donation. When blood is removed, the body draws on its iron stores to make new red cells, and so the excess is gradually "emptied out". 25
The plan has two phases: an emptying phase (about 500 ml of blood every 1-2 weeks until ferritin drops below 50 µg/L) and then a maintenance phase (one session every 2-4 months to keep ferritin around 50-100 µg/L). In the few people who can't tolerate phlebotomy, chelation drugs that trap iron are an alternative. 2
The message that really matters
If overload is detected and treated before cirrhosis or diabetes appear, life expectancy is essentially that of the general population: fatigue improves, liver damage is halted, and even heart involvement can be reversed. The one loose end is that, once cirrhosis is present, the risk of liver cancer persists, so those patients need lifelong monitoring. 112
Key point: the earlier it's caught, the simpler the treatment and the better the outcome. Here, time is on the side of whoever gets checked sooner.
Red flags: when not to let it slide
A high ferritin is rarely urgent, but see a doctor without delay (and mention the iron workup) if you also have:59
- High transferrin saturation (above 45-50%) together with the high ferritin.
- Very high ferritin (above 1000 µg/L).
- Marked fatigue, joint pain (especially in the knuckles) or new-onset diabetes with no clear cause.
- Erectile dysfunction or early loss of periods that don't fit your age.
- A first-degree relative (parent, sibling) with hemochromatosis or iron overload.
- Persistently high liver enzymes or signs of liver disease.
How I approach this in clinic
A high ferritin is one of the most common reasons people arrive at my clinic frightened after a routine blood test. Almost always my job is the opposite of frightening: it's to bring order. I look at the transferrin saturation, review weight, the liver, alcohol and family history, and in the vast majority of cases the problem turns out to be a perfectly manageable fatty liver or metabolic syndrome.
And when hemochromatosis does need ruling out, we do it properly and without drama: the workup is simple and, treated in time, the outlook is excellent. If you have a high ferritin and don't know what it means in your case, we can go over it together, calmly.
In person or online, with your blood test in hand.
Related reading (blood tests that scare but are rarely serious)


A personal note
In clinic I see every day how a single word found online — "hemochromatosis" — turns a routine blood test into a sleepless night. My aim with this guide is for you to reach your appointment with the information in order: knowing what to look at, understanding why there's almost always a reassuring reason, and recognizing the few situations that really do deserve a closer look.

FAQ: quick questions about high ferritin
Does having high ferritin mean I have too much iron?
Not necessarily. Ferritin is a protein that stores iron, but it is also an acute-phase reactant: it rises with inflammation, liver disease, alcohol or metabolic syndrome, without any real excess of iron in the body. In fact, around 90% of people with high ferritin do not have iron overload. That's why a high ferritin is never read on its own: the test that clarifies whether there is true overload is transferrin saturation. 1
What's the most common cause of high ferritin?
In everyday practice, the most common cause of a moderately high ferritin is metabolic syndrome and fatty liver (what is called dysmetabolic hyperferritinemia), together with alcohol and any inflammatory process. In these cases ferritin is high but transferrin saturation is usually normal, because there is no true iron overload. Hereditary hemochromatosis is a far less common cause. 3
When should the genetic test for hemochromatosis (HFE) be done?
The HFE genetic test (C282Y mutation) is recommended when ferritin and transferrin saturation are both high (typically above 45%), not for any isolated high ferritin. If transferrin saturation is normal, the cause is usually metabolic, alcohol-related or inflammatory, and the genetic test is not needed up front. 5
If I have the hemochromatosis gene, will I definitely get sick?
No. Penetrance is incomplete: having the gene is not the same as having the disease. In a population study that followed people with the classic form (C282Y homozygotes), only 28% of men and 1% of women developed iron-overload disease. And when overload is detected and treated in time, before cirrhosis or diabetes appear, life expectancy is normal. 8
References (clickable)
- Koperdanova M, Cullis JO. Interpreting raised serum ferritin levels. BMJ (2015). PMID: 26239322 (opens in a new tab)
- European Association for the Study of the Liver (EASL). EASL Clinical Practice Guidelines on haemochromatosis. J Hepatol (2022). PMID: 35662478 (opens in a new tab)
- Sandnes M, Ulvik RJ, Vorland M, Reikvam H. Hyperferritinemia — A Clinical Overview. J Clin Med (2021). Full text (PMC) (opens in a new tab)
- Cullis JO, Fitzsimons EJ, Griffiths WJH, Tsochatzis E, Thomas DW; British Society for Haematology. Investigation and management of a raised serum ferritin. Br J Haematol (2018). PMID: 29672840 (opens in a new tab)
- Kowdley KV, Brown KE, Ahn J, Sundaram V. ACG Clinical Guideline: Hereditary Hemochromatosis. Am J Gastroenterol (2019). PMID: 31335359 (opens in a new tab)
- Pilling LC, Tamosauskaite J, Jones G, et al. Common conditions associated with hereditary haemochromatosis genetic variants: cohort study in UK Biobank. BMJ (2019). PMID: 30651232 (opens in a new tab)
- Adams PC, Reboussin DM, Barton JC, et al.; HEIRS Study Research Investigators. Hemochromatosis and iron-overload screening in a racially diverse population. N Engl J Med (2005). PMID: 15858186 (opens in a new tab)
- Allen KJ, Gurrin LC, Constantine CC, et al. Iron-overload-related disease in HFE hereditary hemochromatosis. N Engl J Med (2008). PMID: 18199861 (opens in a new tab)
- Cabrera E, Crespo G, VanWagner LB. Diagnosis and Management of Hereditary Hemochromatosis. JAMA (2022). PMID: 36346422 (opens in a new tab)
- St Pierre TG, Clark PR, Chua-anusorn W, et al. Noninvasive measurement and imaging of liver iron concentrations using proton magnetic resonance. Blood (2005). PMID: 15256427 (opens in a new tab)
- Niederau C, Fischer R, Pürschel A, Stremmel W, Häussinger D, Strohmeyer G. Long-term survival in patients with hereditary hemochromatosis. Gastroenterology (1996). PMID: 8613000 (opens in a new tab)
Have a high ferritin and don't know what it means?
We review your full blood test — ferritin, transferrin saturation, liver and context — rule out what's important, and leave you with a clear plan, without unnecessary scares.
Book my assessment
Transparency: this article is not sponsored by any company; the recommendations are based on the evidence and the clinical guidelines cited (ACG and EASL).
Gut health, made simple
My guides and updates on digestion and prevention, in your inbox. No spam.