
Hiatal Hernia: Everything You Need to Know in 2026
A clear, up-to-date and no-nonsense guide on why it happens, what symptoms it causes, when to worry and when not to.

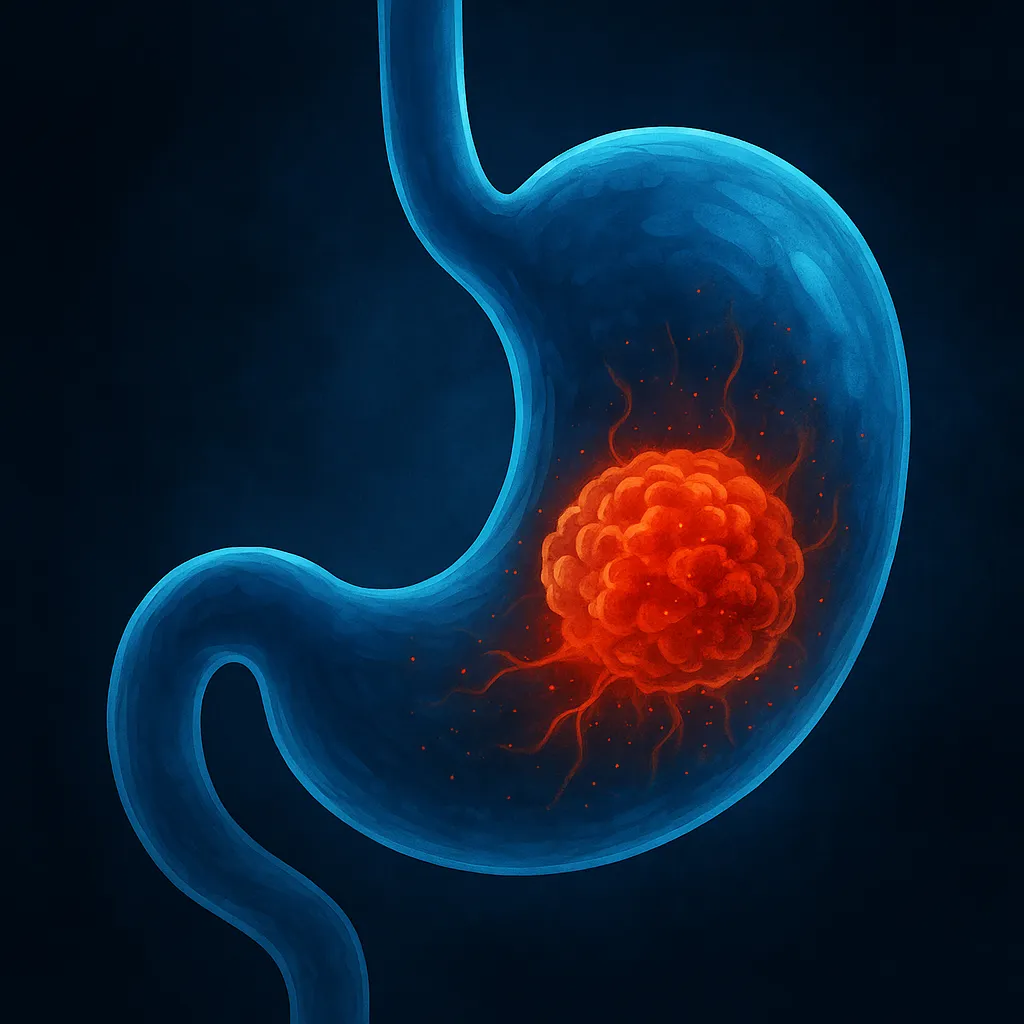
In a hiatal hernia, part of the stomach "sneaks" through the diaphragm opening into the chest.
TL;DR (Quick Summary)
The essentials:
- • Extremely common: found in 95% of studied reflux patients.
- • Most are small, Type I ("sliding") and don't cause serious problems.
- • It won't heal on its own, but many don't need surgery.
What matters:
- • If reflux persists, monitoring is key because it can promote Barrett's esophagus.
- • Surgery is reserved for cases with unresponsive symptoms or complications.
- • Endoscopy is essential to assess actual damage and guide decisions.
Hiatal hernia: everything you need to know in 2026 starts right here, with something I want to make crystal clear from the very first line—having a hiatal hernia is not a catastrophe. It's one of the most common things I see in my clinic, and the vast majority of the time it's manageable. But that doesn't mean you shouldn't understand it. So let's get into it, no unnecessary jargon, just the science behind it explained in plain language.
Quick Index
What exactly is a hiatal hernia?
Picture your body having a "wall" that separates your chest from your abdomen—that's the diaphragm. This wall has a natural opening through which the esophagus (the tube from your throat to your stomach) passes. That opening is called the esophageal hiatus.
When part of your stomach "sneaks" through that opening upward into your chest… that's a hiatal hernia. A 2024 systematic review analyzing over 12,000 patients confirmed that this condition remains one of the most common in gastroenterology, although it's often inaccurately classified in the clinical literature. 1
Types of hiatal hernia: not all are the same
The 4 types (Skinner and Belsey classification):
- Type I – Sliding (83% of cases): the junction between esophagus and stomach slides upward. The most common and most closely linked to reflux.
- Type II – Paraesophageal: part of the stomach moves up alongside the esophagus, but the junction stays in place. Less common, but potentially more dangerous.
- Type III – Mixed: a combination of both.
- Type IV – Giant: besides the stomach, other organs (like the colon) can move into the chest. Rare, but serious.
The one you've likely been diagnosed with (or will see on your endoscopy report) is Type I. Take a breath. It's the most common and the most "well-behaved" of the four. 1
Why does it happen? Causes and risk factors
There's no single cause. A hiatal hernia is like a "team of factors" coming together. According to Watson et al. (2022), the main mechanisms include: the pressure difference between the abdomen and the chest, structural changes in the hiatus (from aging, genetics or wear and tear), and esophageal shortening from fibrosis. 2
The risk factors I see most often in my practice:
- Age: over the years, the diaphragm tissues lose firmness. Normal and expected.
- Obesity: abdominal fat increases upward pressure and pushes the stomach through. It's one of the most consistently documented risk factors in the literature. 3
- Genetics: there's documented familial predisposition, with alterations in extracellular matrix proteins and changes in the diaphragmatic crura.
- Pregnancy: temporary increase in intra-abdominal pressure.
- Chronic cough, severe constipation: anything that repeatedly raises abdominal pressure.
Hiatal hernia symptoms (and when there aren't any)
Reassuring fact
Most Type I hiatal hernias are asymptomatic. That means they're there, but they don't bother you. Many people live with them their whole lives without ever knowing.
When symptoms do appear, the most common ones include:
- 🔥 Heartburn: that burning sensation rising from the stomach to the chest. If this sounds familiar, here's a comprehensive guide on gastroesophageal reflux disease (GERD).
- 🔄 Regurgitation: feeling acid or food coming back up into the throat.
- 🍽️ Dysphagia: difficulty swallowing, as if food is "getting stuck."
- 💨 Frequent belching, bloating, upper abdominal or chest pain.
Paraesophageal hernias (Types II–IV) can also cause obstructive symptoms, and in rare cases, gastric volvulus—a surgical emergency. 3
Complications: what to watch out for
This is where a hiatal hernia stops being "just a hernia" and deserves proper attention. Not to scare you, but so you understand why your doctor sometimes insists on follow-up.
1) Barrett's Esophagus
This is the complication patients ask about most (and the one we care most about monitoring). A 2024 meta-analysis with over 131,000 participants showed that hiatal hernia is associated with a 3.91 times higher risk of Barrett's esophagus overall, and up to 10 times higher for long-segment Barrett's. In other words: hiatal hernia is an independent and significant risk factor for this precancerous condition. 4
If you want to understand what Barrett's is and how often to get checked, I recommend reading about endoscopic treatment of Barrett's esophagus.
2) Erosive Esophagitis
A 2023 meta-analysis of 759,100 participants found that hiatal hernia has the highest odds ratio (4.07) among all risk factors for erosive esophagitis. Higher than obesity, higher than age. In short: it's the number one risk factor. 5
3) Other Complications
Less common but real: ulcers at the gastroesophageal junction, esophageal strictures (narrowing), iron-deficiency anemia from Cameron lesions, and in large or paraesophageal hernias, the dreaded gastric volvulus (an emergency).
When to seek emergency care:
If you experience sudden, severe chest pain, can't swallow anything (not even liquids), vomit blood, or have persistent vomiting with inability to eat—go to the emergency room. It could be a volvulus or an acute complication.
How is a hiatal hernia diagnosed?
The gold-standard tool is an upper GI endoscopy (gastroscopy). It lets us directly visualize the hernia's size and type, check for esophagitis, Barrett's, and take biopsies if needed. It's the preferred method according to the ACG GERD guidelines. 6
Other useful tests
- • Barium swallow (esophagram): ideal for assessing size before surgery.
- • High-resolution esophageal manometry: measures how your esophagus moves (important if surgery is being considered).
- • pH monitoring: measures how much acid reaches the esophagus over 24 hours.
- • CT scan of chest and abdomen: for large hernias or suspected complications like volvulus.
If you need a thorough evaluation with a high-quality endoscopy, you can request a private endoscopy appointment in Madrid.
Diagnosed with a hiatal hernia and have questions? Bring your report and let's review it together.
Hiatal hernia treatment: from lifestyle to surgery
Step 1: Lifestyle changes (yes, they really matter)
This isn't filler advice: losing weight if you're overweight, not eating late at night, elevating the head of your bed, and avoiding foods that worsen reflux (fatty foods, spicy meals, alcohol, excessive coffee). It sounds basic, but for small hernias with mild reflux, this alone can sometimes be enough.
Step 2: Medical treatment
Proton pump inhibitors (PPIs: omeprazole, pantoprazole, esomeprazole…) remain the pharmacological cornerstone for managing associated reflux. Antacids and prokinetics can complement treatment in some cases.
Step 3: Surgery (when it's time)
The gold standard is laparoscopic repair with cruroplasty (closing the diaphragm opening) plus fundoplication (creating a new anti-reflux valve using the stomach itself). The 2024 SAGES guidelines conditionally recommend routine fundoplication during hiatal hernia repair. 7
What about mesh? Yes or no?
Hot topic. A 2025 network meta-analysis suggests that non-absorbable mesh with fundoplication may have the lowest recurrence rate, but the quality of evidence is very low. Each case is individualized. 8
Endoscopic option: Transoral Incisionless Fundoplication (TIF)
For patients with refractory GERD and hernias between 2–5 cm, transoral incisionless fundoplication (TIF) with simultaneous repair is showing PPI discontinuation rates of up to 73.8% with a favorable safety profile. It's a less invasive alternative to traditional laparoscopic surgery. 9
Special case: obesity + hiatal hernia
In patients with severe obesity and hiatal hernia with GERD, Roux-en-Y gastric bypass is considered the best surgical option, as it addresses both problems simultaneously. Sleeve gastrectomy with simultaneous hernia repair also significantly improves reflux symptoms. 10
Related reads you'll find useful


This is also medicine: warmth and trust
Behind every hiatal hernia diagnosis is a person with questions, sometimes with fear, and almost always with contradictory information from the internet. My job is to cut through the noise, give you a clear diagnosis and a plan that makes sense for you. If you're reading this and have questions, the door is open.

FAQ: Frequently asked questions about hiatal hernia
Can a hiatal hernia heal on its own?
It doesn't disappear on its own. But most are small and manageable with lifestyle changes and, if needed, medication. Surgery is only considered when there are complications or stubborn symptoms.
Does having a hiatal hernia mean I'll get cancer?
No. It can promote reflux and, in some cases, Barrett's esophagus. But with proper monitoring and treatment, the risk is well controlled. It's not a death sentence. 4
Can I exercise with a hiatal hernia?
Yes. Avoid exercises that significantly increase abdominal pressure right after eating (intense crunches, heavy deadlifts after dinner). Regular moderate exercise is actually beneficial.
When does a hiatal hernia need surgery?
When reflux can't be controlled with medication, complications develop (Barrett's, severe esophagitis, anemia) or the hernia is large with risk of volvulus. The 2024 SAGES guidelines are clear on this. 7
What's the connection between hiatal hernia and reflux?
Very direct. The hernia displaces the anti-reflux valve (lower esophageal sphincter), making it less effective. In studies, up to 95% of patients with documented GERD had an associated hiatal hernia. 11
References (clickable)
- Fuchs KH, Kafetzis I, Hann A, Meining A. Hiatal Hernias Revisited—A Systematic Review of Definitions, Classifications, and Applications. J Clin Med (2024). Full text (PMC)
- Watson DI, Lally CJ. The Pathogenesis of Hiatal Hernia. Annals of Laparoscopic and Endoscopic Surgery (2022). Access article
- Yu HX, Han CS, Xue JR, et al. Esophageal hiatal hernia: risk, diagnosis and management. Expert Rev Gastroenterol Hepatol (2018). PubMed: 29451037
- Ma S, et al. Association between hiatal hernia and Barrett's esophagus: an updated meta-analysis with trial sequential analysis. Therap Adv Gastroenterol (2024). Full text (PMC)
- Witarto AP, Samarta B, et al. Risk factors and 26-years worldwide prevalence of endoscopic erosive esophagitis from 1997 to 2022: a meta-analysis. BMC Gastroenterol (2023). Full text (PMC)
- Katz PO, Dunbar KB, Schnoll-Sussman FH, et al. ACG Clinical Guideline for the Diagnosis and Management of Gastroesophageal Reflux Disease. Am J Gastroenterol (2022). PubMed: 34807007
- Daly S, Kumar SS, Collings AT, et al. SAGES guidelines for the surgical treatment of hiatal hernias. Surg Endosc (2024). PubMed: 39080063
- Weiss S, Emile SH, et al. Evaluating surgical outcomes of hiatal hernia repair techniques with and without fundoplication: a network meta-analysis. Surg Endosc (2025). PubMed: 40629013
- Concomitant hiatal hernia repair with transoral incisionless fundoplication. Surg Endosc (2024). PubMed: 39271515
- El Nakeeb A, et al. Outcomes of Concomitant Laparoscopic Sleeve Gastrectomy and Hiatal Hernia Repair. Obes Surg (2025). PubMed: 40205116
- Fuchs KH, et al. Pathophysiology of gastroesophageal reflux disease—which factors are important? Transl Gastroenterol Hepatol (2021). Full text (PMC)
Have a hiatal hernia and need a clear plan?
Bring your endoscopy report. In the consultation, we'll review what type of hernia you have, whether there are complications, and decide together on the next steps.
Book an Appointment