
Anal conditions · Practical guide
Hemorrhoids and anal fissure: what really works
How to tell them apart, which treatments have been shown to help (and which have not), the most repeated myths, and the one sign you should never take for granted.
 Dr. Pedro de María · Gastroenterologist
August 4, 2026
~14 min
16 references (PubMed and ASCRS guidelines)
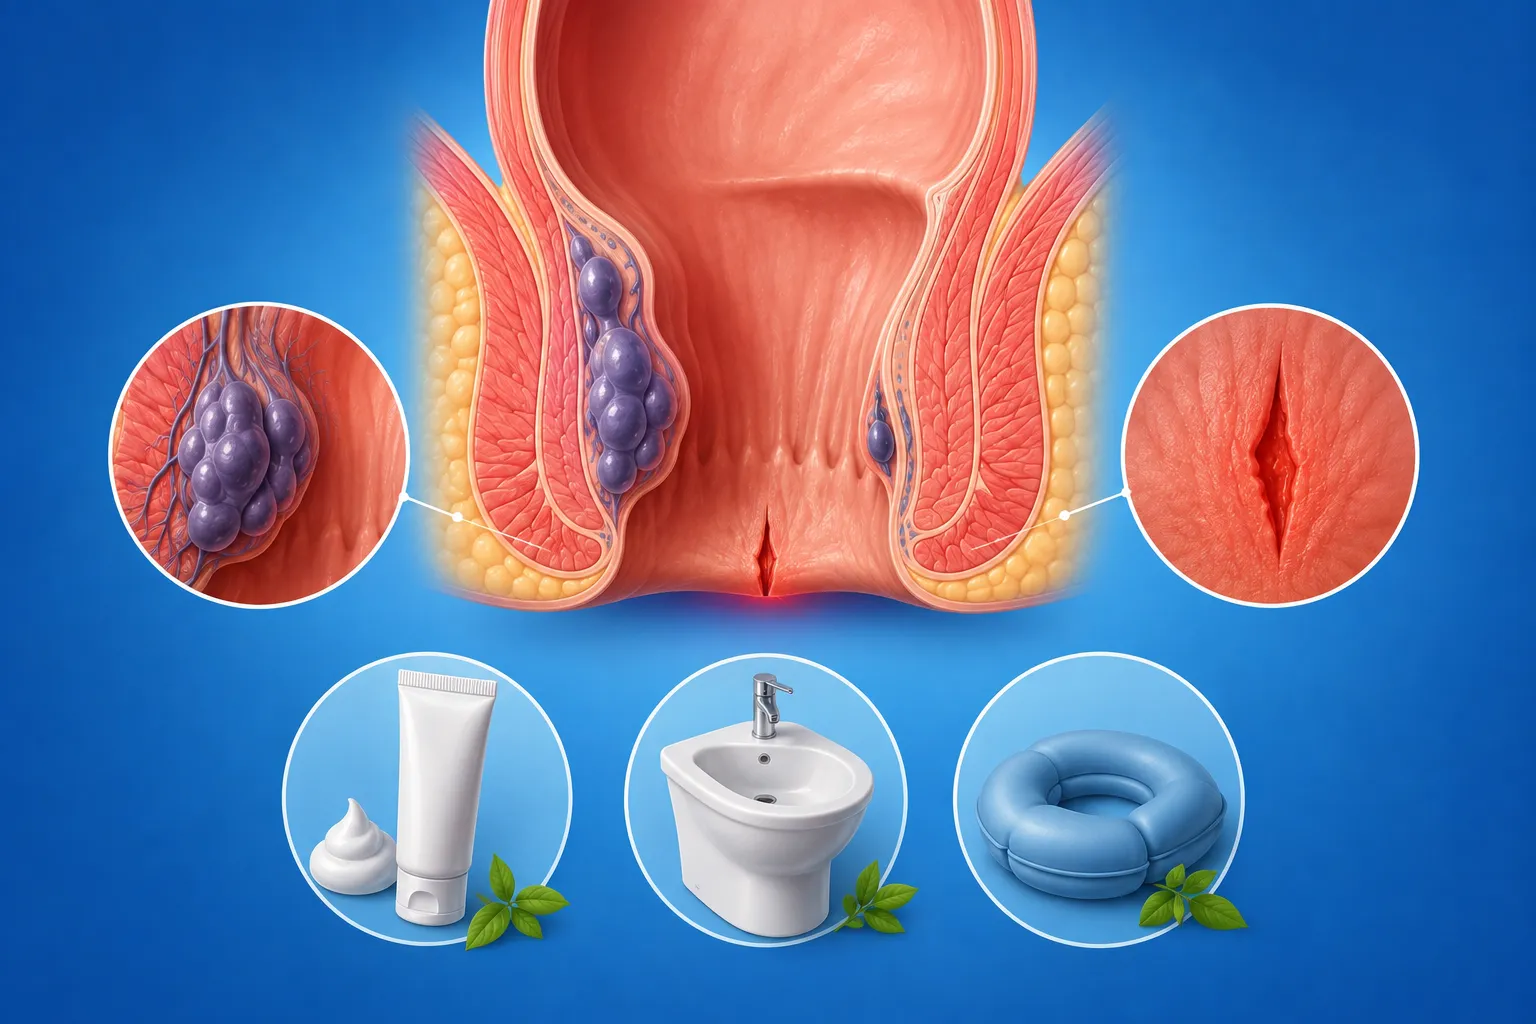
Hemorrhoids and anal fissures get confused all the time, but one detail separates them: pain. Hemorrhoids usually bleed without hurting much; a fissure hurts a great deal when you pass stool. And the treatment that actually works is not the same for both.
For both, the foundation is identical and it is the single most effective thing there is: fiber and water (it halves the risk of bleeding). From there, for hemorrhoids that keep bleeding what changes things most is rubber band ligation; for a fissure, an ointment that relaxes the sphincter. And one important warning: having hemorrhoids does not prove they are the cause of the bleeding.
~39%
of adults have hemorrhoids at screening colonoscopy; more than half have no symptoms
–50%
risk of bleeding, just by increasing fiber
Blood ≠
hemorrhoids
having them doesn't prove they're the cause: it has to be looked at
Informational guide: it does not replace your doctor's assessment and is not a way to diagnose yourself. Any bleeding from the anus should be assessed by a professional.
This is one of the most common reasons for a consultation, and also one that people put off the longest out of embarrassment. Which is a shame, because most of these problems have a simple solution and almost never need surgery. The aim of this guide is for you to know what you have, what actually works according to the evidence, and when it needs investigating rather than being treated blindly.
1Part 1 of 6
How to tell which is which
Although they share the same area, they are different things. Hemorrhoids are cushions of veins that we all have inside the anus and that help with continence; the problem starts when they become dilated, bleed or prolapse. An anal fissure is something else: a small tear at the edge of the anus, almost always in the midline, which hurts as it is pulled open with every bowel movement.
The detail that helps most to tell them apart is how much it hurts:
| Internal hemorrhoids | Anal fissure | |
|---|---|---|
| Pain | Little or none; more discomfort, heaviness or itching | Severe, sharp, during and after passing stool |
| Bleeding | Bright red, drips at the end or stains the paper | Small amount, red, on the paper |
| How long the pain lasts | — | Can carry on for minutes or hours |
| Other signs | A lump that comes out and goes back in; itching | Fear of going to the toilet, which worsens constipation |
Internal hemorrhoids are classified by grade, and this matters because it decides the treatment: grade I only bleed; grade II prolapse on straining but go back on their own; grade III have to be pushed back manually; grade IV can no longer be reduced. 2 If itching is your main problem, something else may be going on: I cover it in the article on anal itching. And if the pain comes in brief stabs unrelated to passing stool, it may be neither of the two, but proctalgia fugax.
2Part 2 of 6
Why they happen (and how common they are)
Far more common than people think. In an Austrian study that examined almost a thousand people attending for screening colonoscopy, 39% had hemorrhoids, and the most striking part: more than half had no symptoms at all. Most were grade I. The study also found that a high body mass index was an independent risk factor. 1
The common thread behind almost everything is straining to pass stool: hard stools, pushing, and spending a long time sitting on the toilet. In a fissure there is also a very characteristic vicious circle: the tear hurts, the pain makes the sphincter contract, that contraction reduces blood supply to the area and makes healing harder; and because it hurts, the person holds on and becomes more constipated, so the next bowel movement tears it open again. Breaking that circle is exactly what treatment aims to do. 3
Key idea: if you don't fix the constipation and the straining, no local treatment is going to last. That is why many "relapses" are not relapses at all, but the cause still being there.
3Part 3 of 6
The foundation for both: fiber and water
It sounds unspectacular, but it is the measure with the best evidence in this whole article. A meta-analysis of 7 trials with 378 patients showed that increasing fiber reduces the risk of persisting symptoms by 47% and — most importantly — halves the risk of bleeding. The effect held up at follow-up at 6 weeks and at 3 months. 4 For prolapse, pain and itching, on the other hand, the results were less conclusive: fiber is above all the anti-bleeding measure.
What you should actually do (and it costs little)
- Fiber up to about 25-30 g a day, increasing gradually so you don't get bloated, and drinking water: without fluid, fiber makes constipation worse. If you need help, here is the constipation guide and the natural remedies.
- Don't strain. If nothing comes in a minute, get up and come back later.
- No phone in the bathroom. Sitting on the toilet for a long time is one of the habits that contributes most.
- Go when you feel the urge, without holding on: holding on hardens the stool. On what is normal, I explain it here: how often you should poop.
- Gentle hygiene: water, and pat dry without rubbing. Avoid perfumed wipes and harsh soaps, which irritate.
4Part 4 of 6
Hemorrhoids: what works, by grade
Creams and suppositories. They relieve, but they don't solve. Steroid ones calm itching and inflammation and should be used in short courses (one or two weeks), because used long-term they thin the skin in the area; local anesthetic ones take the pain away for a few hours. They are symptomatic support, not the underlying treatment. 2
Phlebotonics (the "venotonics", such as diosmin and flavonoids). There is more evidence here than many people think: a Cochrane review of 24 studies found a significant benefit for bleeding and for overall symptom improvement, and also for itching. The review itself does warn about methodological limitations in the trials, so they are best seen as a reasonable help during flare-ups, not as the definitive solution. 5
Rubber band ligation. This is the most worthwhile office treatment for grade I-III hemorrhoids that keep bleeding: a band is placed at the base of the hemorrhoid, it takes a few minutes, needs no admission and is practically painless. It is not surgery, and it lets you go back to normal life almost immediately. 2
Banding or surgery: the honest trade-off
Surgery cures more, but it hurts more. A recent Dutch trial in grade III quantified this very well: recurrence was 47.5% with banding versus 6.1% with surgery, but pain in the first week was greater with surgery and return to work was 1 day with banding versus 9 with surgery. 7 This is in line with the classic Cochrane review (surgery controls symptoms better, especially in grade III, whereas in grade II there was no clear difference) 6 and with a later meta-analysis: better control with surgery, but at the cost of more pain and more complications, with similar patient satisfaction in both groups. 8
Translated: in grade II it usually makes sense to start with banding; in grade III it is a shared decision between doctor and patient, depending on how much you care about avoiding time off work versus the possibility of needing a repeat procedure.
5Part 5 of 6
Anal fissure: the key is relaxing the sphincter
Since the problem is that the contracted sphincter stops the tear from healing, treatment consists of relaxing it chemically while the stool is softened. The two classic ointments are glyceryl trinitrate and 2% diltiazem, applied twice a day for 6 to 12 weeks.
Which to choose? A meta-analysis of 9 trials compared them head to head: they heal almost identically, but diltiazem is much better tolerated — headaches were dramatically less frequent — and it had fewer late relapses. That is why it tends to be preferred as the first option. 11 A 2025 network meta-analysis of 22 trials points the same way: nifedipine achieved the highest healing rate, followed by diltiazem, which was the best for pain control and had the lowest recurrence, while glyceryl trinitrate caused the most adverse effects. 12
It helps to know what to expect. The Cochrane review that pooled 75 trials and more than 5,000 patients was honest: glyceryl trinitrate heals somewhat better than placebo (48.9% versus 35.5%), but late recurrence is common, around half of those initially healed; botulinum toxin and calcium channel blockers are equivalent to glyceryl trinitrate with fewer adverse effects; and no medical treatment matches surgery, although none of them carries its risk of incontinence either. 10
If the ointment fails, two steps remain: botulinum toxin, which relaxes the sphincter for a few months without cutting anything, and lateral internal sphincterotomy, which is the reference operation. Comparing them, a meta-analysis of 18 trials with 1,839 patients confirmed that surgery heals more than botulinum toxin. 13 The trade-off is the small but real risk of affecting control of gas and stool, which is why the decision is individualized. 3
Key idea: with a fissure, the ointment almost never works if you don't sort out the stool. Fiber and water are not "filler advice": they are half the treatment.
6Part 6 of 6
When surgery is needed (and the real risk)
Surgery is not the enemy, but it is not the first step either. It is considered for grade III-IV hemorrhoids, when banding fails, or when bleeding is significant and repeated; in a fissure, when it has become chronic and does not respond to medical treatment. 23
The fear people express most in my clinic is ending up incontinent. That deserves an answer with numbers: a systematic review of 139 studies with more than 30,000 patients found that, after hemorrhoid surgery, incontinence occurred in 5.3% early on (first 3 months) and in 2.5% later in the randomized trials, with no clear difference between classic hemorrhoidectomy and the stapled technique. In other words: it is uncommon, but it is not zero, and that is why surgery should be reserved for those who genuinely need it. 9
Myths and facts
These are the five I hear most, and what the evidence says about each.
Myth: "Spicy food makes hemorrhoids worse"
Fact, with a caveat: for hemorrhoids it is false. A randomized crossover trial in 50 patients with grade II-III compared a chili pepper capsule against placebo and found no worsening whatsoever of symptoms: there is no reason to stop you enjoying a spicy dish now and then.14 But careful: with an acute fissure it is the other way round. In a similar trial, chili did increase pain and burning, and 81% of patients preferred the placebo.15 If you have a raw fissure, leave it for later.
Myth: "Sitz baths cure it"
Fact: they soothe, but they don't cure. In a randomized trial in acute fissure, sitz baths did not significantly improve either pain or healing, although they did improve patient satisfaction; two people also developed skin irritation.16 Use them for comfort if they suit you, not as treatment.
Myth: "You get them from sitting on cold surfaces"
Fact: there is nothing to support this. What does matter is straining to pass stool, hard stools, time spent sitting on the toilet and excess weight, which has been identified as an independent risk factor.1
Myth: "If I'm bleeding, it must be the hemorrhoids"
Fact: this is the most dangerous mistake in the whole article. Hemorrhoids are so common — 39% of the population, most without symptoms — that finding them does not prove they are the cause of the bleeding.1 A polyp or a tumour can bleed in exactly the same way, and colon cancer is rising in young people. Here is the detail on the causes of blood in the stool.
Myth: "Sooner or later you'll need an operation"
Fact: most people never have surgery. Grades I-II are managed well with fiber, habits and, if they bleed, rubber band ligation; and a good proportion of fissures close with ointment and soft stools. Surgery is reserved for the cases that do not respond.23
Warning signs: when NOT to settle for "it's just hemorrhoids"
Ask for your colon to be investigated, not just your anus, if any of these appear:
- Blood that is dark or mixed in with the stool (not just when you wipe).
- A change in your bowel habit lasting more than 3-4 weeks.
- Weight loss you weren't trying for, fatigue, or anemia on a blood test.
- A family history of colon cancer or polyps, or already being at screening age.
- Bleeding that does not improve within 2-3 weeks of correct treatment.
- A lump that will not go back in, or sudden severe pain with a hard nodule (this may be a thrombosis).
- A fissure that is not in the midline or that will not heal despite treatment: this means other causes must be ruled out, such as Crohn's disease or an infection.3
My approach in clinic
My job here is twofold. First, to put a name to the problem with a simple examination — which is quick and considerably less uncomfortable than people fear — and to decide whether we need to look higher up with a colonoscopy, which is my field. Many cases of bleeding have been labelled "hemorrhoids" for months without anyone having examined them, and that is exactly what I don't want for you.
And second, to treat what can be treated: sorting out the constipation, prescribing properly what actually works, and performing rubber band ligation when it is indicated. When a case needs surgery, I refer it to coloproctology, who are the ones who perform it. If you have had discomfort or bleeding for a while, don't put it off out of embarrassment: it is one of the most rewarding consultations there is.
In-person or online consultation, and a colonoscopy if your case calls for it.
Related reading



A personal note
Of all the consultations I see, this is the one where embarrassment weighs heaviest and where most time is lost. And that is a double shame: because there is almost always a simple solution, and because sometimes behind bleeding "from hemorrhoids" there is something that should have been looked at sooner. If this sounds like you, book an appointment. It is a two-minute examination that can save you years of discomfort — or something more important.

Frequently asked questions
How do I know whether I have hemorrhoids or an anal fissure?
The main clue is pain. Internal hemorrhoids usually cause bright red blood at the end of a bowel movement, dripping or staining the paper, and they feel uncomfortable or itchy, but they barely hurt. An anal fissure is a small tear at the edge of the anus and it hurts a lot: a sharp, cutting pain during the bowel movement that can keep hurting for minutes or hours afterwards, with a little blood on the paper. Put simply: bleeding without pain points to hemorrhoids, and severe pain on passing stool points to a fissure. The only way to confirm it is an examination, which is simple and quick. 3
Which cream actually works for hemorrhoids?
Creams relieve the symptom, but they are not the treatment that changes things the most. The ones containing a steroid calm itching and inflammation, although they should only be used in short courses of one or two weeks because over time they thin the skin; the ones containing a local anesthetic relieve pain for a few hours. What has actually been shown to reduce symptoms, and above all bleeding, is increasing fiber and drinking water, which halves the risk of bleeding. If the problem is repeated bleeding, the most effective next step is not another cream but rubber band ligation. 4
Can an anal fissure heal without surgery?
Yes, many fissures heal without surgery, especially recent ones. The foundation is softening the stool with fiber and water to break the cycle of pain and constipation, and adding an ointment that relaxes the sphincter, usually 2% diltiazem or glyceryl trinitrate, for 6 to 12 weeks. Both heal equally well, but diltiazem causes far fewer headaches and fewer relapses, which is why it is usually preferred. If the fissure becomes chronic and does not close, the next step is botulinum toxin or surgery, which heals more but carries a small risk of affecting control of gas and stool. 11
Is bleeding when passing stool always hemorrhoids?
No, and this is the mistake that worries me most. Hemorrhoids are so common that almost anyone can have some, so finding them does not prove they are the cause of the bleeding: a polyp or a colon cancer can bleed in exactly the same way. It must be investigated whenever the blood is dark or mixed in with the stool, if your bowel habit changes for more than three or four weeks, if there is weight loss or anemia, if you have a family history of colon cancer, if you have reached screening age, or if the bleeding does not improve within two or three weeks of treatment. When in doubt, the answer is to look. 1
References (clickable)
- Riss S, Weiser FA, Schwameis K, et al. The prevalence of hemorrhoids in adults. Int J Colorectal Dis (2012). PMID: 21932016 (opens in a new tab)
- Hawkins AT, Davis BR, Bhama AR, et al. The American Society of Colon and Rectal Surgeons Clinical Practice Guidelines for the Management of Hemorrhoids. Dis Colon Rectum (2024). PMID: 38294832 (opens in a new tab)
- Davids JS, Hawkins AT, Bhama AR, et al. The American Society of Colon and Rectal Surgeons Clinical Practice Guidelines for the Management of Anal Fissures. Dis Colon Rectum (2023). PMID: 36321851 (opens in a new tab)
- Alonso-Coello P, Mills E, Heels-Ansdell D, et al. Fiber for the treatment of hemorrhoids complications: a systematic review and meta-analysis. Am J Gastroenterol (2006). PMID: 16405552 (opens in a new tab)
- Perera N, Liolitsa D, Iype S, et al. Phlebotonics for haemorrhoids. Cochrane Database Syst Rev (2012). PMID: 22895941 (opens in a new tab)
- Shanmugam V, Thaha MA, Rabindranath KS, et al. Rubber band ligation versus excisional haemorrhoidectomy for haemorrhoids. Cochrane Database Syst Rev (2005). PMID: 16034963 (opens in a new tab)
- van Oostendorp JY, Dekker L, Sluckin TC, et al. Comparison of Rubber Band Ligation and Hemorrhoidectomy in Patients With Symptomatic Hemorrhoids Grade III: A Multicenter, Open-Label, Randomized Controlled Noninferiority Trial. Dis Colon Rectum (2025). PMID: 39952268 (opens in a new tab)
- Dekker L, Han-Geurts IJM, Rørvik HD, et al. Rubber band ligation versus haemorrhoidectomy for the treatment of grade II-III haemorrhoids: a systematic review and meta-analysis of randomised controlled trials. Tech Coloproctol (2021). PMID: 33683503 (opens in a new tab)
- Jin JZ, Bhat S, Park B, et al. The prevalence of incontinence after excisional hemorrhoidectomy and stapled hemorrhoidopexy: A systematic review and meta-analysis. Surgery (2025). PMID: 39854786 (opens in a new tab)
- Nelson RL, Thomas K, Morgan J, Jones A. Non surgical therapy for anal fissure. Cochrane Database Syst Rev (2012). PMID: 22336789 (opens in a new tab)
- Nevins EJ, Kanakala V. Topical diltiazem and glyceryl-trinitrate for chronic anal fissure: A meta-analysis of randomised controlled trials. Turk J Surg (2020). PMID: 33778393 (opens in a new tab)
- Wang C, et al. The efficacy of diltiazem, glyceryl trinitrate, nifedipine, minoxidil, and lidocaine for the medical management of anal fissure: a systematic review and network meta-analysis of randomized controlled trials. Int J Surg (2025). PMID: 39878173 (opens in a new tab)
- Bonyad A, et al. Botulinum toxin injection versus lateral internal sphincterotomy for chronic anal fissure: a meta-analysis of randomized control trials. Langenbecks Arch Surg (2024). PMID: 39579232 (opens in a new tab)
- Altomare DF, Rinaldi M, La Torre F, et al. Red hot chili pepper and hemorrhoids: the explosion of a myth: results of a prospective, randomized, placebo-controlled, crossover trial. Dis Colon Rectum (2006). PMID: 16708161 (opens in a new tab)
- Gupta PJ. Consumption of red-hot chili pepper increases symptoms in patients with acute anal fissures. Ann Ital Chir (2008). PMID: 19149363 (opens in a new tab)
- Gupta P. Randomized, controlled study comparing sitz-bath and no-sitz-bath treatments in patients with acute anal fissures. ANZ J Surg (2006). PMID: 16916391 (opens in a new tab)
Had discomfort or bleeding for a while?
We put a name to the problem with a simple examination, rule out what matters, and treat what actually works in your case.
Book an appointment
Transparency: this article is not sponsored. The recommendations are based on the evidence and the clinical guidelines cited. Surgical treatment is performed by coloproctology specialists.
Digestive health, made simple
My guides and updates on digestion and prevention, straight to your inbox. No spam.