
Functional Heartburn: The Burning That Won't Go Away
You've had burning behind your chest for months, you've tried omeprazole and every test comes back normal. This is the updated 2026 guide (with the new Rome V criteria) to understand what's happening and what works.

By Dr. Pedro de María Pallarés
Specialist in Gastroenterology
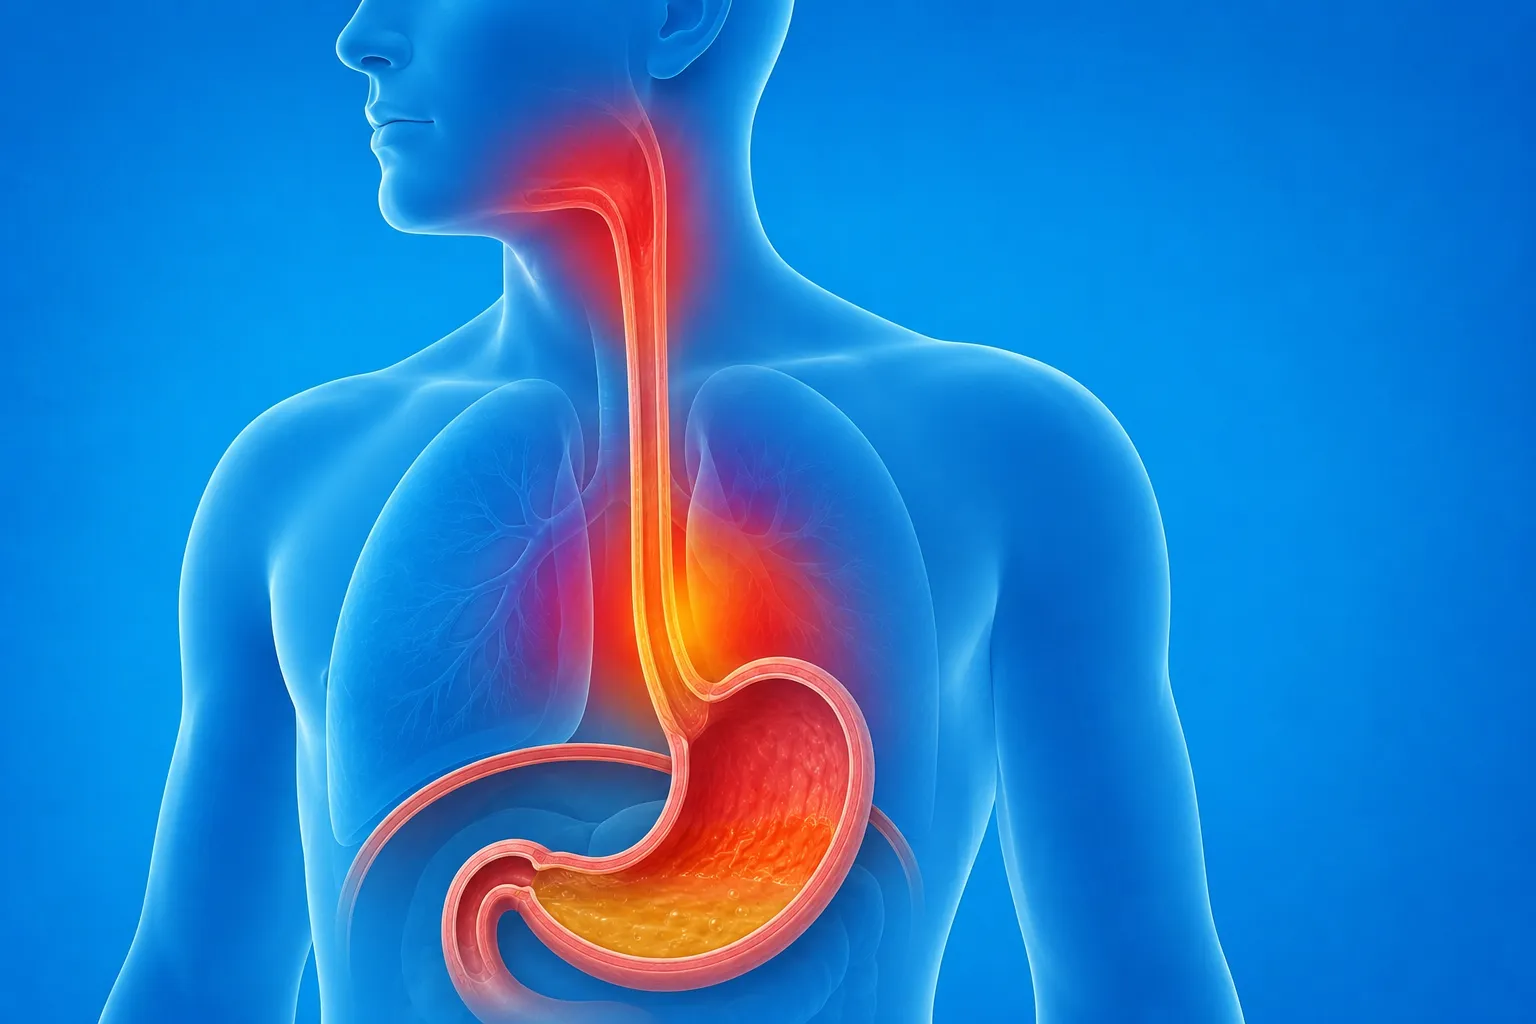
In functional heartburn there is real burning, but the esophagus is healthy and no acid reflux is found to explain it.
TL;DR (quick summary)
What is it?
- Retrosternal burning that does not improve with antacids and with normal tests.
- A disorder of gut–brain interaction (Rome V, 2026 criteria): a healthy but hypersensitive esophagus.
What is done?
- Tell it apart from GERD with pH-impedance (Lyon Consensus).
- Treat the gut–brain axis (hypnotherapy, CBT), not the acid.
Is it serious? No: it is benign and in some cases improves on its own. But it is worth confirming the diagnosis and checking the warning signs.
Functional heartburn is burning or pain behind the chest that persists despite optimal acid-suppressing treatment, when the endoscopy, the biopsies and the acid measurement are normal and there is no reflux to explain it. In other words: the esophagus is healthy, but hypersensitive. Under the international Rome V criteria (the 5th edition, published in 2026) it is an esophageal disorder of gut–brain interaction. 12
Quick index
What is functional heartburn? (Rome V)
"Heartburn" is simply the medical term for that retrosternal burning. Functional heartburn is one of the five functional esophageal disorders (now called disorders of gut–brain interaction), alongside functional chest pain, reflux hypersensitivity, functional dysphagia and pharyngeal globus. In 2026 Rome V was published, the 5th edition of these criteria, which keeps functional heartburn in this group and, for the first time, synchronizes the Rome and Lyon consensuses to define in a modern way what is reflux and what is not. 134
The underlying idea is that the nerves connecting the esophagus to the brain work in a hypersensitive way: the brain interprets as "burning" signals that in another person would go unnoticed. That is why it is a real disorder (not "imaginary") even though the tests come back fine. 1
Why doesn't omeprazole work for me?
Because in functional heartburn the problem is not acid. Proton pump inhibitors (omeprazole, esomeprazole, pantoprazole…) reduce acid, but if acid is not the cause, there is nothing to improve. In fact, functional heartburn is the most common cause of heartburn that does not respond to these drugs: more than half of people with persistent heartburn despite taking PPIs twice a day actually have functional heartburn (or its cousin, reflux hypersensitivity). 910
Taking omeprazole "just in case" doesn't help
The AGA clinical practice update is clear: in pure functional heartburn, PPIs have no therapeutic value (unless GERD also coexists and is proven). Keeping them indefinitely without objective reflux does not solve the burning and just adds medication. That said, don't stop them on your own: the diagnosis must be confirmed first. I explain it in does omeprazole cause cancer?. 6
Functional heartburn vs GERD vs reflux hypersensitivity
This is the key to modern diagnosis. Three conditions can cause the same burning, but they are different and treated differently. They are told apart by measuring esophageal acid over 24 hours (pH-impedance), with the Lyon Consensus thresholds that Rome V has incorporated: 71
| Condition | What the acid tests show |
|---|---|
| True GERD | There is too much acid in the esophagus: acid does explain the symptoms and they respond to antacids. |
| Reflux hypersensitivity | Acid is normal, but symptoms coincide with reflux episodes: the esophagus overreacts to normal reflux. |
| Functional heartburn | Acid is normal and there is no link between symptoms and reflux: the burning is not explained by acid. |
The distinction matters because it drives treatment: GERD benefits from antacids (and from treating peptic esophagitis or a hiatal hernia if present), whereas functional heartburn and reflux hypersensitivity go more down the hypersensitivity route. A real caveat: the conditions can overlap (there are patients with functional heartburn who have also had GERD), so they are not always watertight compartments. 12
Why does it happen?
The central mechanism is esophageal hypersensitivity: the esophagus perceives normal stimuli as painful. Added to that are hypervigilance (being very aware of chest sensations) and anxiety, which amplify the perception. It is not that "it's just nerves" in a dismissive sense: it is that the system processing the esophagus's signals is sensitized. 1
In fact, in manometry studies, esophageal hypervigilance and visceral anxiety were the strongest predictors of symptom severity, with twice the weight of having an esophageal motility disorder. Understanding this changes the treatment approach. 11
Warning signs: when to seek care without waiting
"Functional" burning is benign, but these symptoms require investigation (with endoscopy) before labeling it functional:68
- Difficulty or pain when swallowing.
- Unintentional weight loss.
- Vomiting blood or black stools.
- Unexplained anemia or iron deficiency.
- New symptoms after age 50–60 or that worsen rapidly.
How is it diagnosed?
Functional heartburn is a diagnosis that requires ruling out everything else. According to Rome V and the AGA guidance, you have to confirm that: 16
- The burning persists despite optimal acid-suppressing treatment taken correctly.
- The endoscopy with biopsies is normal (rules out esophagitis and eosinophilic esophagitis).
- The acid measurement (pH-impedance) is normal and symptoms are not associated with reflux.
- There are no major esophageal motility disorders (assessed with manometry).
The test that really decides is the 24-hour pH-impedance, ideally off acid-suppressing treatment, because it is the one that separates functional heartburn from GERD and reflux hypersensitivity. If you are going to have a gastroscopy, here I explain the preparation. 57
Treatment: what works (and what doesn't)
Since the driver is not acid but hypersensitivity, the treatment changes focus:
1. Understand the diagnosis (and drop what doesn't help)
Knowing that the esophagus is healthy and that the condition is benign already helps a lot: in a proportion of patients functional heartburn improves on its own (around 40% in some series). The first step is usually to withdraw, in an orderly way, the antacids that are not adding anything. 106
2. Gut–brain axis therapies (the best supported)
Gut–brain-directed therapies are today the treatment with the most support. A 2024 expert consensus places esophagus/gut-directed hypnotherapy as a recommended initial therapy, and cognitive behavioral therapy (CBT) as an appropriate option. They are not "for the nerves": they act on the hypersensitivity and on how the brain processes the esophagus's signals. 15
3. Neuromodulators (in selected cases)
Low-dose neuromodulators (tricyclic antidepressants such as amitriptyline, or SSRIs/SNRIs) aim to "turn down the volume" of visceral pain perception. Here it is worth being honest: the evidence in functional heartburn specifically is limited and inconsistent —a 2024 meta-analysis found them more useful in functional chest pain and globus than in functional heartburn, and a trial with imipramine did not beat placebo—. That is why they are reserved for selected cases and always individualized. 1314
If the test confirms reflux hypersensitivity (instead of pure functional heartburn), combining an antacid + a neuromodulator does make more sense. And if an associated functional dyspepsia appears (overlap is common), it is addressed together. 7
My approach in the clinic
Many patients arrive frustrated after years of antacids that don't take the burning away, with the feeling that "nothing is found". My priority is to put a name to the problem: confirm with the acid test whether it is GERD, reflux hypersensitivity or functional heartburn, because the whole treatment depends on that.
When it is functional heartburn, the shift in mindset is huge: we stop chasing acid and work on the hypersensitivity with explanation, gut–brain axis therapies and, if needed, a neuromodulator. Most people improve once the approach finally matches what is really happening to them.
If you have had burning that won't go away with anything for a while, we can find out why and give it the right approach.
Related reading (to complete the picture)


A personal touch (yes, this is medicine too)
Few things are more frustrating than burning that won't go away and a "there's nothing wrong with you". My commitment is to show that there is an explanation —it's just not acid— and to offer a plan that genuinely matches what you feel.

FAQ: quick questions about functional heartburn
What is functional heartburn?
It is burning or pain behind the chest that persists despite optimal acid-suppressing treatment, when the tests (endoscopy, biopsies and acid measurement) are normal and there is no reflux to explain it. Under the Rome V (2026) criteria it is an esophageal disorder of gut-brain interaction: the esophagus is healthy but hypersensitive. 1
Why doesn't omeprazole take my heartburn away?
Because in functional heartburn the problem is not acid, but a hypersensitivity of the esophagus. That is why proton pump inhibitors usually do not work in pure functional heartburn, and it is in fact the most common cause of heartburn that does not respond to these drugs. 6
How is it different from GERD and reflux hypersensitivity?
They are told apart with pH-impedance. In true GERD there is too much acid in the esophagus. In reflux hypersensitivity the acid is normal but symptoms coincide with reflux episodes. In functional heartburn the acid is normal and there is no link between symptoms and reflux. 7
Does functional heartburn have treatment, or does it go away?
It is benign and in a proportion of patients it improves on its own. What works best are gut-brain-directed therapies (hypnotherapy and CBT) and reassuring explanation; low-dose neuromodulators can help in selected cases, with more limited evidence. 15
References (clickable)
- Gyawali CP, Roman S, Zerbib F, et al. Functional Esophageal Disorders (Rome V). Gastroenterology (2026). PMID: 42031441 (opens in a new tab)
- Drossman DA, Chang L, Tack J. Disorders of Gut-Brain Interaction and the Rome V Process. Gastroenterology (2026). PMID: 42031435 (opens in a new tab)
- The Rome Foundation. Rome V, Disorders of Gut-Brain Interaction (5th Edition) (2026). Rome Foundation (opens in a new tab)
- Aziz Q, Fass R, Gyawali CP, et al. Functional Esophageal Disorders (Rome IV, comparison base). Gastroenterology (2016). PMID: 27144625 (opens in a new tab)
- Rome IV Diagnostic Criteria for Functional Heartburn (diagnostic criteria). MDCalc. Criteria (MDCalc) (opens in a new tab)
- Fass R, Zerbib F, Gyawali CP. AGA Clinical Practice Update on Functional Heartburn: Expert Review. Gastroenterology (2020). PMID: 32017911 (opens in a new tab)
- Gyawali CP, Yadlapati R, Fass R, et al. Updates to the modern diagnosis of GERD: Lyon consensus 2.0. Gut (2024). Full text (PMC) (opens in a new tab)
- Katz PO, Dunbar KB, Schnoll-Sussman FH, et al. ACG Clinical Guideline for the Diagnosis and Management of GERD. Am J Gastroenterol (2022). PMID: 34807007 (opens in a new tab)
- Yamasaki T, O'Neil J, Fass R. Update on Functional Heartburn. Gastroenterol Hepatol (N Y) (2017). Full text (PMC) (opens in a new tab)
- Gabbard S, Vijayvargiya S. Functional heartburn: an underrecognized cause of PPI-refractory symptoms. Cleve Clin J Med (2019). View article (opens in a new tab)
- Carlson DA, Gyawali CP, Roman S, et al. Esophageal Hypervigilance and Visceral Anxiety Are Contributors to Symptom Severity. Am J Gastroenterol (2020). Full text (PMC) (opens in a new tab)
- Rengarajan A, Pomarat M, Zerbib F, Gyawali CP. Overlap of functional heartburn and reflux hypersensitivity with proven GERD. Neurogastroenterol Motil (2021). PMID: 33300667 (opens in a new tab)
- Limsrivilai J, Charatcharoenwitthaya P, Pausawasdi N, Leelakusolvong S. Imipramine for Esophageal Hypersensitivity and Functional Heartburn: A Randomized Placebo-Controlled Trial. Am J Gastroenterol (2016). PMID: 26753892 (opens in a new tab)
- Yeh JH, Chen CL, Sifrim D, et al. Central neuromodulators for patients with functional esophageal disorders: a systematic review and meta-analysis. Dig Liver Dis (2024). PMID: 38851975 (opens in a new tab)
- Guadagnoli L, Yadlapati R, Pandolfino J, et al. Behavioral Therapy for Functional Heartburn: Recommendation Statements. Clin Gastroenterol Hepatol (2024). Full text (PMC) (opens in a new tab)
Burning that won't go away with anything? Let's find out why
We confirm whether it is GERD, reflux hypersensitivity or functional heartburn, and design the treatment that truly fits you.
Book my assessment
Transparency: this article is not sponsored by any pharmaceutical company; the recommendations are based on the cited evidence.